


Athlete’s heart is a constellation of structural and functional changes that occur in the heart of people who train for prolonged durations (eg, > 1 hour most days) and/or frequently at high intensities. The changes, including increased left ventricular wall thickness and/or chamber size, are asymptomatic; signs include bradycardia, a systolic murmur, and extra heart sounds. Electrocardiographic (ECG) abnormalities are common. Diagnosis is clinical or by echocardiography. No treatment is necessary. Athlete's heart is significant because it must be distinguished from serious cardiac disorders.
Exercise-induced cardiac remodelling (EICR) and athlete's heart are terms that can be used interchangeably. This condition results when there is repetitive and sustained exercise exposure. The exercise dose and nature of the sport may determine the structural changes that are observed in the heart of these individuals (1). Volume and pressure loads in the left ventricle (LV) increase, which, over time, increase LV muscle mass, wall thickness, and chamber size. Maximal stroke volume and cardiac output increase, contributing to a lower resting heart rate and longer diastolic filling time. Lower heart rate results primarily from increased vagal tone, but decreased sympathetic activation and other nonautonomic factors that decrease intrinsic sinus node activity may play a role. Bradycardia decreases myocardial oxygen demand; at the same time, increases in total hemoglobin and blood volume enhance oxygen transport. Despite these changes, systolic function and diastolic function remain normal. Structural changes in females are typically less than those in males of the same age, body size, and level of training (2, 3).
Atrial fibrillation risk in athletes
Numerous studies have found an increased risk of developing atrial fibrillation in patients who participate in endurance and mixed sports (4, 5). Athletes younger than 55 years are at higher risk. The specific dose of exercise at which the risk increases has not been documented in high quality studies.
Coronary artery calcification and mortality in athletes
Increased lifelong exercise volume, a measure of cumulative physical activity typically expressed as metabolic equivalent (MET) minutes per week, appears to have a non-linear association with coronary artery calcification (CAC). Individuals with very high lifelong exercise volumes (> 2000 to 3000 MET minutes/week) are more likely to have CAC scores > 100 Agatston units (6, 7). Compared to scores in their less active peers, CAC is more common in male but not female endurance athletes. For males with CAC scores < 100 Agatston units, those performing the highest volume of activity had a lower mortality rate compared to less active peers. For males with Agatston scores ≥ 100, there was no difference in event rates between individuals with a high volume of activity and those with a low volume. Furthermore, for any given CAC score category, males with higher fitness levels had lower cardiovascular risk compared to those with lower levels. However, when CAC score ≥ 400 is compared to CAC score of 0, even individuals with the greatest fitness with scores ≥ 400 have a greater cardiovascular risk than the least fit with a CAC score of 0.
General references
1. Hsieh PN, Shen S, Chukwurah MI, et al. Athlete's Heart Revisited: Historical, Clinical, and Molecular Perspectives. Circ Res. 2025;137(2):231-254. doi:10.1161/CIRCRESAHA.125.325638
2. Lampert R, Chung EH, Ackerman MJ, et al. 2024 HRS expert consensus statement on arrhythmias in the athlete: Evaluation, treatment, and return to play. Heart Rhythm. 2024;21(10):e151-e252. doi:10.1016/j.hrthm.2024.05.018
3. Martinez MW, Kim JH, Shah AB, et al. Exercise-induced cardiovascular adaptations and approach to exercise and cardiovascular disease. JACC State-Of-The-Art Review. J Am Coll Cardiol. 2021;78(14): 1454-1470. doi: 10.1016/j.jacc.2021.08.003
4. La Gerche A, Wasfy MM, Brosnan MJ, et al. The Athlete's Heart-Challenges and Controversies: JACC Focus Seminar 4/4. J Am Coll Cardiol. 2022;80(14):1346-1362. doi:10.1016/j.jacc.2022.07.014
5. Newman W, Parry-Williams G, Wiles J, et al. Risk of atrial fibrillation in athletes: a systematic review and meta-analysis. Br J Sports Med. 2021;55(21):1233-1238. doi:10.1136/bjsports-2021-103994
6. DeFina LF, Radford NB, Barlow CE, et al. Association of all-cause and cardiovascular mortality with high levels of physical activity and concurrent coronary artery calcification. JAMA Cardiol. 2019;4(2):174-181. doi:10.1001/jamacardio.2018.4628
7. Eijsvogels TMH, Kim JH, Aengevaeren VL, et al. Masters Athletes With Abnormal Cardiovascular Findings: A Clinical Consensus Statement of the European Association of Preventive Cardiology of the ESC and the American College of Cardiology. J Am Coll Cardiol. Published online April 6, 2026. doi:10.1016/j.jacc.2026.03.025
Symptoms and Signs of Athlete’s Heart
There are no symptoms. Signs vary but may include:
Bradycardia
An LV impulse that is laterally displaced, enlarged, and increased in amplitude
A systolic ejection (flow) murmur at the left lower sternal border
A third heart sound (S3) due to early, rapid diastolic ventricular filling
Hyperdynamic carotid pulses


These signs reflect structural cardiac changes that are adaptive for intense exercise.
The presence of a fourth heart sound (S4) is almost always abnormal in an athlete.
Diagnosis of Athlete’s Heart
History and physical examination
Usually ECG
Sometimes echocardiography
Rarely, cardiac magnetic resonance imaging
Rarely, stress testing
Findings are typically detected during routine screening or during evaluation of unrelated symptoms. Most athletes do not require extensive testing, although ECG is often warranted. If symptoms suggest a cardiac disorder (eg, palpitations, chest pain), ECG, echocardiography, and exercise stress testing are performed.
Athlete's heart is a diagnosis of exclusion; it must be distinguished from disorders that cause similar findings but are life threatening (eg, hypertrophic cardiomyopathy, dilated cardiomyopathy, ischemic heart disease (commonly caused by coronary artery disease), arrhythmogenic right ventricular cardiomyopathy—[1]). Cardiac magnetic resonance (CMR) imaging may be helpful when findings from other diagnostic modalities are inconclusive. Sometimes a trial of deconditioning is required to differentiate athlete's heart from cardiomyopathy.
ECG
Numerous changes in rhythm and ECG morphology can occur; they correlate poorly with level of training and cardiovascular performance. The most common ECG finding is:
Sinus bradycardia
Rarely, heart rate is < 40 beats/minute. Sinus arrhythmia often accompanies the slow heart rate. Resting bradycardia may also predispose to:
Atrial or ventricular ectopy (including couplets and bursts of nonsustained ventricular tachycardia); pauses after ectopic beats do not exceed 4 seconds
Wandering atrial (supraventricular) pacemaker
Other ECG findings that may occur include (2, 3):
Second-degree type I AV block; this finding occurs during rest and disappears with exercise
High-voltage QRS with inferolateral T-wave changes (reflecting LV hypertrophy)
Deep anterolateral T-wave inversion
Incomplete right bundle branch block
Profound first-degree AV block (PR interval ≥ 400 msec), second degree type 2 AV block, and third-degree AV block are considered abnormal and should be investigated thoroughly. Guidelines exist for classifying electrocardiographic findings in athletes as normal versus abnormal (2).
These ECG and rhythm changes have not clearly been associated with adverse clinical events, suggesting that various arrhythmias are not abnormal in athletes ( 3, 4). The arrhythmias are often abolished or substantially reduced after a relatively brief period of deconditioning (5).
International Consensus Standards for Electrocardiographic Interpretation in Athletes
ECG Finding | Evaluation Required |
|---|---|
Normal findings | |
Isolated voltage criteria for left or right ventricular hypertrophy Incomplete right bundle branch block ST segment elevation consistent with early repolarization ST elevation followed by T wave inversion in leads V1–V4, in Black athletes T wave inversion in V1–V3 age in athletes < 16 years old Sinus bradycardia (≥ 30 bpm) or sinus arrhythmia Ectopic atrial or junctional rhythm Low-grade AV block (first-degree, or second-degree Type 1 AV block with PR 200–399 ms) | No further evaluation required* |
Borderline findings | |
Left axis deviation Right axis deviation Left atrial enlargement Right atrial enlargement Complete right bundle branch block | In isolation: No further evaluation required* 2 or more borderline criteria present: Further evaluation required |
Abnormal findings | |
T-wave inversion (except as noted under "normal findings") ST segment depression Pathologic Q waves Complete left bundle branch block Non-specific intraventricular conduction delay with QRS ≥ 140 ms duration Epsilon wave Ventricular pre-excitation Prolonged QT interval Brugada type 1 pattern Sinus bradycardia < 30 bpm First-degree AV block with PR interval ≥ 400 msec Second-degree type II or third-degree AV block ≥ 2 premature ventricular contractions Atrial tachyarrhythmias Ventricular arrhythmias | Further evaluation required |
*If asymptomatic, and no family history of sudden cardiac death or inherited cardiac disease | |
AV = atrioventricular; bpm = beats per minute. | |
Sharma S, Drezner JA, Baggish A, et al. International Recommendations for Electrocardiographic Interpretation in Athletes. J Am Coll Cardiol. 2017;69(8):1057-1075. doi:10.1016/j.jacc.2017.01.015 | |
Echocardiography
Echocardiography can usually distinguish athlete’s heart from cardiomyopathies (see table ), but the distinction is not always clear because there is a continuum from physiologic to pathologic cardiac enlargement. The zone of overlap (gray zone) between athlete’s heart and cardiomyopathy is left ventricular septal thickness (6, 7):
In males, 13 to 15 mm
In females, 11 to 13 mm
In this overlap area, the presence of mitral valve systolic anterior motion strongly suggests hypertrophic cardiomyopathy (8). Also, diastolic indices may be abnormal in cardiomyopathy but are usually normal in athlete's heart (9). For example, The measurement of e' may be a particularly useful measure of diastolic function because it is less preload dependent than the E:A ratio (9). In this gray zone, assessment of systolic function with left ventricular global longitudinal strain measurement may further assist to differentiate athlete's heart from a cardiomyopathy (10, 11). Balanced 4-chamber enlargement favors athlete's heart rather than a cardiomyopathy (10). In general, however, echocardiographic changes correlate poorly with level of training and cardiovascular performance (10, 11).
Exercise echocardiography may help to differentiate athlete's heart from dilated cardiomyopathy (12). In one study, a change during exercise in left ventricular ejection fraction (LVEF) ≤ 11% and a peak LVEF ≤ 63% during exercise predicted dilated cardiomyopathy with a sensitivity of 85.7% and specificity of 92%.
Cardiac magnetic resonance imaging
When an echocardiogram does not definitely exclude pathology in an athlete, a cardiac MRI can be helpful to differentiate athlete's heart from a cardiomyopathy (1, 13). In hypertrophic cardiomyopathy, cardiac MRI may identify focal hypertrophy not identified on the echocardiogram, particularly in the apex, anterior free wall, and posterior septum (14). Delayed imaging after injection of contrast may show a typical pattern of mid-wall fibrosis in some patients with hypertrophic cardiomyopathy, particularly in left ventricular wall segments that exhibit maximal hypertrophy. However, this finding is absent in up to 60% of patients with hypertrophic cardiomyopathy.
Delayed enhancement on cardiac MRI is also evident in nonischemic dilated cardiomyopathy and may help differentiate dilated cardiomyopathy from athlete's heart. However, the finding is absent in 68% of patients with genetically proven dilated cardiomyopathy. T1 and T2 mapping, extracellular volume quantification, late gadolinium enhancement, deformation imaging and diffusion tensor imaging are all promising techniques to differentiate between athlete's heart and hypertrophic cardiomyopathy. Further studies are required to better determine the ability of these techniques to detect hypertrophic cardiomyopathy in athletes (13, 15).
Although exercise capacity as measured by stress testing does not differentiate between athlete's heart and dilated cardiomyopathy, reduced cardiac contractile reserve with exercise observed on CMR imaging may be useful in establishing a diagnosis of dilated cardiomyopathy in an athlete.
Stress testing
Exercise-stress testing (EST) is a widely available functional test that can be performed using a treadmill or cycle-ergometer. The test provides information about symptoms, blood pressure, heart rate, and ECG changes. During EST, the heart rate in athletes remains lower than normal at submaximal stress and increases appropriately and comparably to heart rate in nonathletes at maximal stress. After exercise, the heart rate rapidly recovers to the pretest rate. The systolic blood pressure increases with exercise but generally does not exceed 220 mm Hg in males and 200 mm Hg in females. Diastolic blood pressure generally falls, while an increase above 85 mm Hg in males and greater than 80 mm Hg in females is considered an unusual response.

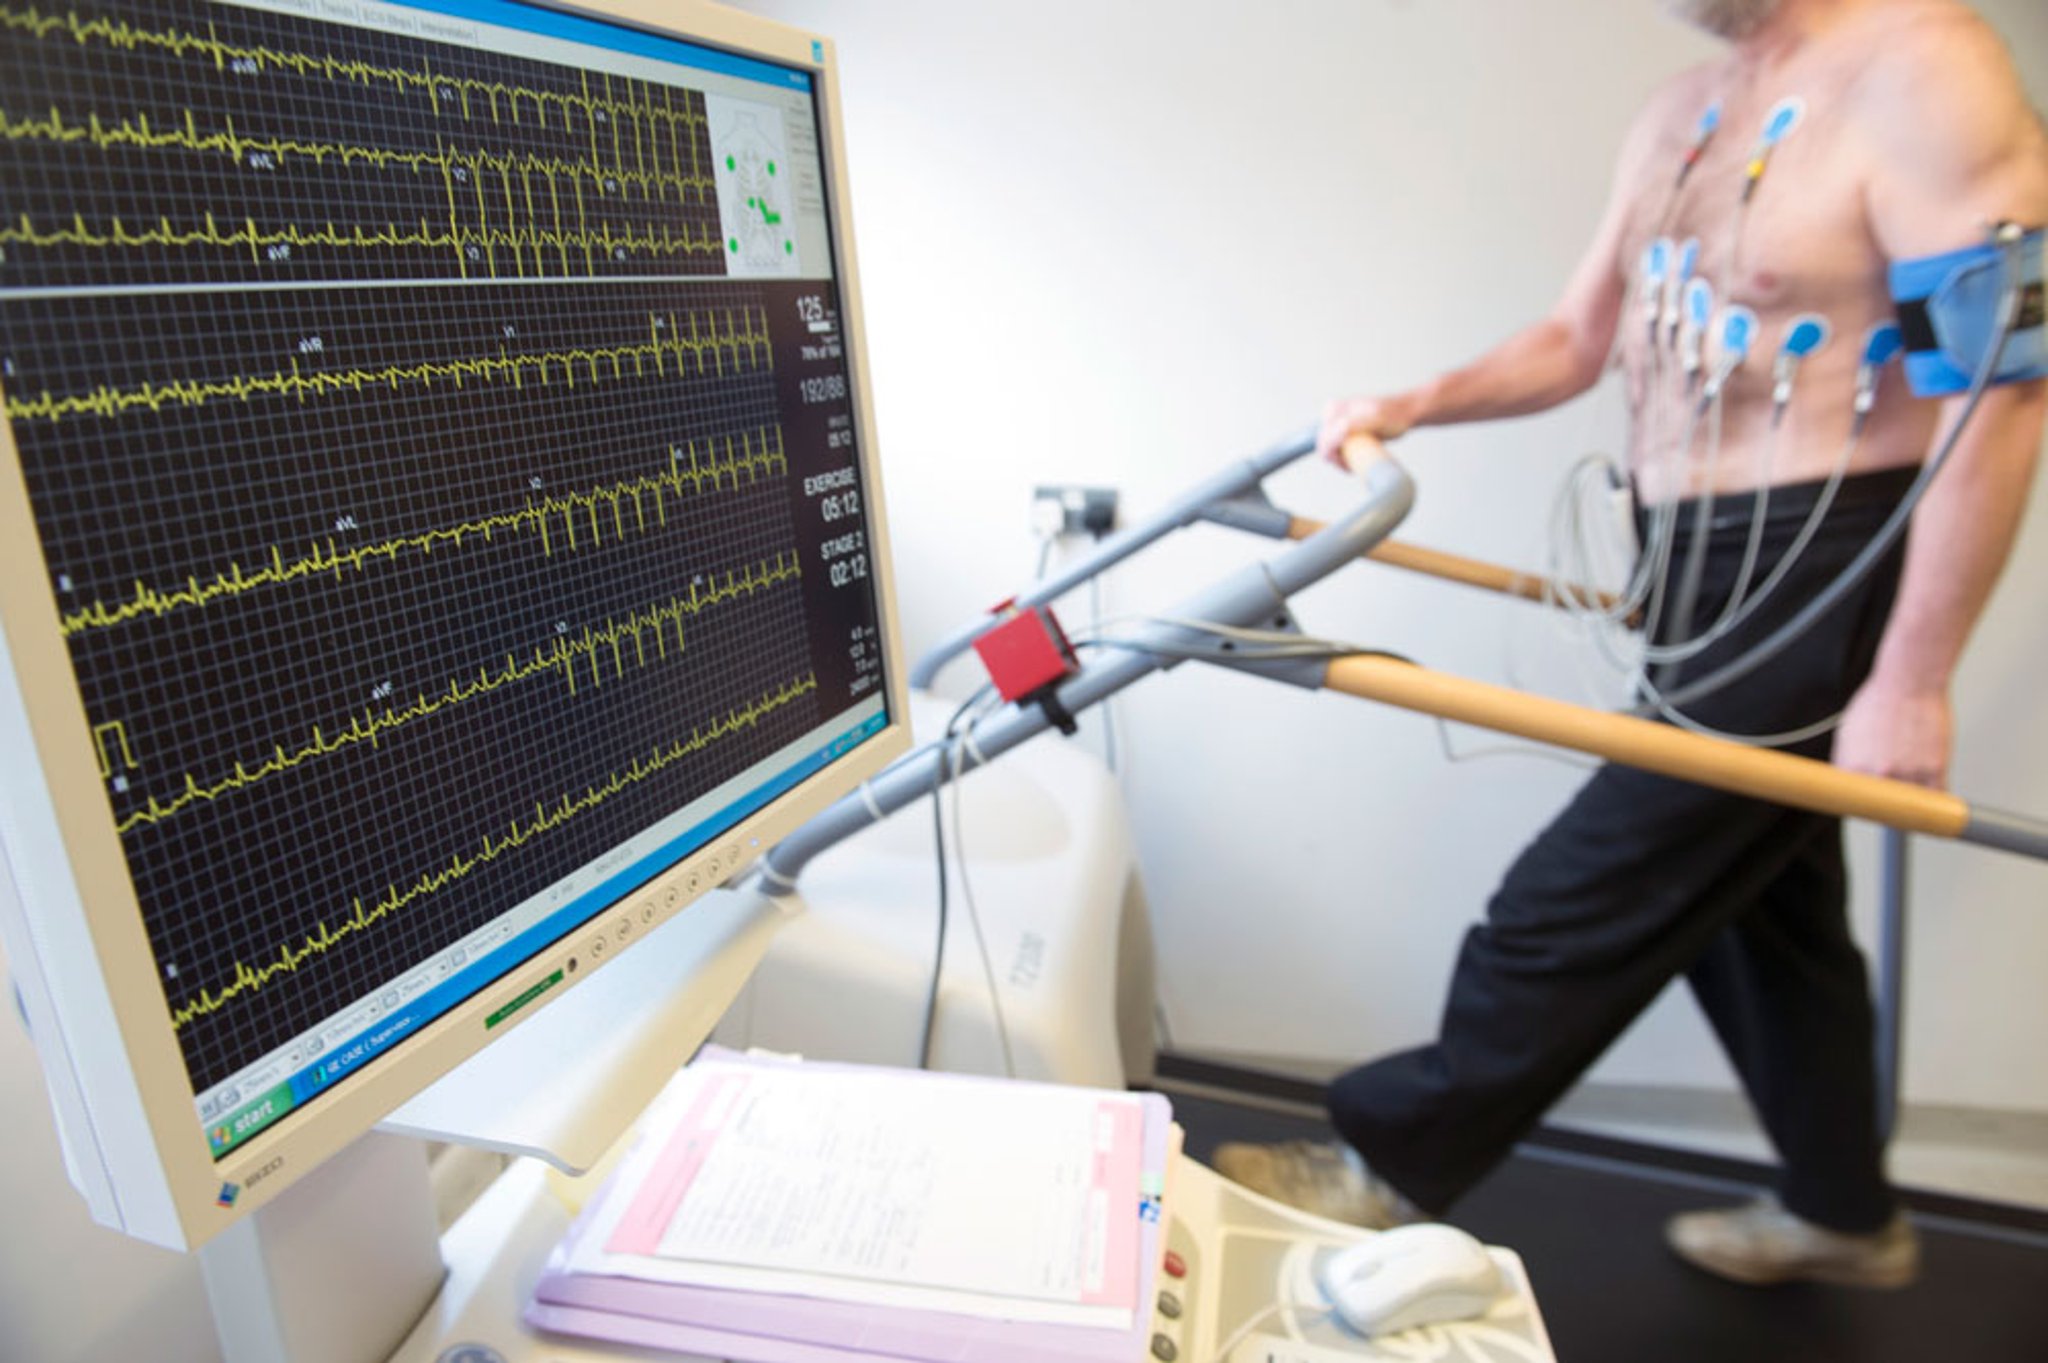
In this photo, a patient walks on a treadmill attached to multiple ECG electrodes; ECG monitoring and recording equipment is in the foreground.
DR P. MARAZZI/SCIENCE PHOTO LIBRARY
Many resting ECG variations decrease or disappear during exercise; this finding is unique to athlete's heart, distinguishing it from pathologic conditions. However, pseudonormalization of T-wave inversions could reflect myocardial ischemia warranting further investigation in older athletes.
The cardiopulmonary exercise test (CPET) combines the components of the EST with respiratory gas exchange measurements. The test can evaluate overall functional capacity as well as the response of the cardiac, pulmonary, vascular, and musculoskeletal systems to symptom-limited (or maximal) exercise. The use of the CPET to assess the athlete's physiological response to exercise can assist in differentiating between the diagnosis of athlete's heart versus an underlying cardiovascular condition (1)
Also, a normal exercise stress test result does not exclude a cardiomyopathy.
Features Distinguishing Athlete's Heart From Cardiomyopathy
Feature | Athlete’s Heart | Cardiomyopathy |
|---|---|---|
Left ventricular septal thickness* | In males, < 13 mm In females, < 11 mm | In males, > 15 mm In females, > 13 mm |
Left ventricular end-diastolic diameter† | < 60 mm | > 70 mm |
Diastolic function | Normal (E:A ratio > 1‡) septal e' ≥ 10 cm/sec lateral e' ≥ 12 cm/sec | Abnormal (E:A ratio < 1) septal e' < 10 cm/sec lateral e' < 12 cm/sec |
Systolic function | Global longitudinal strain more negative than -16% | Global longitudinal strain less negative than -16% |
Septal hypertrophy | Symmetric | Asymmetric (in hypertrophic cardiomyopathy) |
Family history of cardiomyopathy or sudden cardiac death | None | May be present |
Blood pressure response to exercise | Normal | Normal or reduced systolic blood pressure response |
Deconditioning | Left ventricular hypertrophy regression | No left ventricular hypertrophy regression |
* A value of 13 to 15 mm in males and 11 to 13 mm in females is indeterminate. | ||
† A value of 60 to 70 mm is indeterminate. | ||
‡ E:A ratio = ratio of early to late atrial transmitral flow velocity. | ||
Finocchiaro G, Westaby J, Sheppard MN, Papadakis M, Sharma S. Sudden Cardiac Death in Young Athletes: JACC State-of-the-Art Review. J Am Coll Cardiol. 2024;83(2):350-370. doi:10.1016/j.jacc.2023.10.032 | ||
Diagnosis references
1. Palermi S, Cavarretta E, D’Ascenzi F, et al. Athlete's Heart: A cardiovascular step-by-step multimodality approach. Rev Cardiovasc Med. 2023;24(5):151. https://doi.org/10.31083/j.rcm2405151
2. Sharma S, Drezner JA, Baggish A, et al. International Recommendations for Electrocardiographic Interpretation in Athletes. J Am Coll Cardiol. 2017;69(8):1057-1075. doi:10.1016/j.jacc.2017.01.015
3. Zipes DP, Link MS, Ackerman MJ, et al. Eligibility and Disqualification Recommendations for Competitive Athletes With Cardiovascular Abnormalities: Task Force 9: Arrhythmias and Conduction Defects: A Scientific Statement From the American Heart Association and American College of Cardiology. Circulation. 2015;132(22):e315-e325. doi:10.1161/CIR.0000000000000245
4. Lampert R, Chung EH, Ackerman MJ, et al. 2024 HRS expert consensus statement on arrhythmias in the athlete: Evaluation, treatment, and return to play. Heart Rhythm. 2024;21(10):e151-e252. doi:10.1016/j.hrthm.2024.05.018
5. Biffi A, Maron BJ, Verdile L, et al. Impact of physical deconditioning on ventricular tachyarrhythmias in trained athletes. J Am Coll Cardiol. 2004;44(5):1053-1058. doi:10.1016/j.jacc.2004.05.065
6. Caselli S, Maron MS, Urbano-Moral JA, Pandian NG, Maron BJ, Pelliccia A. Differentiating left ventricular hypertrophy in athletes from that in patients with hypertrophic cardiomyopathy. Am J Cardiol. 2014;114(9):1383-1389. doi:10.1016/j.amjcard.2014.07.070
7. Churchill TW, Petek BJ, Wasfy MM, et al. Cardiac Structure and Function in Elite Female and Male Soccer Players. JAMA Cardiol. 2021;6(3):316-325. doi:10.1001/jamacardio.2020.6088
8. Maron BJ, Desai MY, Nishimura RA, et al. Diagnosis and Evaluation of Hypertrophic Cardiomyopathy: JACC State-of-the-Art Review. J Am Coll Cardiol. 2022;79(4):372-389. doi:10.1016/j.jacc.2021.12.002
9. Finocchiaro G, Westaby J, Sheppard MN, Papadakis M, Sharma S. Sudden Cardiac Death in Young Athletes: JACC State-of-the-Art Review. J Am Coll Cardiol. 2024;83(2):350-370. doi:10.1016/j.jacc.2023.10.032
10. Martinez MW, Kim JH, Shah AB, et al. Exercise-Induced Cardiovascular Adaptations and Approach to Exercise and Cardiovascular Disease: JACC State-of-the-Art Review. J Am Coll Cardiol. 2021;78(14):1453-1470. doi:10.1016/j.jacc.2021.08.003
11. Thomas JD, Edvardsen T, Abraham T, et al. Clinical Applications of Strain Echocardiography: A Clinical Consensus Statement From the American Society of Echocardiography Developed in Collaboration With the European Association of Cardiovascular Imaging of the European Society of Cardiology. J Am Soc Echocardiogr. 2025;38(11):985-1020. doi:10.1016/j.echo.2025.07.007
12. Millar LM, Fanton Z, Finocchiaro G, et al. Differentiation between athlete's heart and dilated cardiomyopathy in athletic individuals. Heart. 2020;106(14):1059-1065. doi: 10.1136/heartjnl-2019-316147
13. Baggish AL, Battle RW, Beaver TA, et al: Recommendations on the use of multimodality cardiovascular imaging in young adult competitive athletes: A report from the American Society of Echocardiography in collaboration with the Society of Cardiovascular Computed Tomography and the Society for Cardiovascular Magnetic Resonance. J Am Soc Echocardiogr 33 (5): 523–549, 2020. doi: 10.1016/j.echo.2020.02.009
14. Czimbalmos C, Csecs I, Toth A, et al. The demanding grey zone: Sport indices by cardiac magnetic resonance imaging differentiate hypertrophic cardiomyopathy from athlete's heart. PLoS ONE. 2019;14(2): e0211624. doi:10.1371/journal.pone.0211624
15. Bakogiannis C, Mouselimis D, Tsarouchas A, et al. Hypertrophic cardiomyopathy or athlete's heart? A systematic review of novel cardiovascular magnetic resonance imaging parameters. Eur J Sports Sci. 2023;23(1):143-154. doi: 10.1080/17461391.2021.2001576
Treatment of Athlete’s Heart
No treatment is required for athlete's heart because it is generally considered a physiological response to high volume exercise.
A period of 8 to 12 weeks of deconditioning has been proposed and used as a way to differentiate between athlete's heart and a cardiomyopathy (1, 2). This recommendation is based on the rationale that changes due to athlete's heart should regress with the cessation of the training stimulus, whereas the cardiomyopathy would persist. This strategy should only be implemented when a thorough evaluation, including ECG, echocardiography, cardiac MRI, CPET, and genetic testing, fails to provide a definitive diagnosis for gray-zone left ventricular hypertrophy. Furthermore, deconditioning requires complete cessation of exercise, which may be impractical and/or unappealing for the athlete, especially given that the optimal duration of detraining is uncertain. When this strategy is used, the results should be interpreted in light of the inherent limitations, including that in some cases there would also be apparent resolution of the cardiomyopathy phenotype in those athletes with a cardiomyopathy.
Treatment references
1. La Gerche A, Wasfy MM, Brosnan MJ, et al. The Athlete's Heart-Challenges and Controversies: JACC Focus Seminar 4/4. J Am Coll Cardiol. 2022;80(14):1346-1362. doi:10.1016/j.jacc.2022.07.014
2. Martinez MW, Kim JH, Shah AB, et al. Exercise-induced cardiovascular adaptations and approach to exercise and cardiovascular disease. JACC State-Of-The-Art Review. J Am Coll Cardiol. 2021;78(14): 1454-1470. doi: 10.1016/j.jacc.2021.08.003
Prognosis for Athlete’s Heart
Although gross structural changes resemble those in some cardiac disorders, generally no adverse effects are apparent. In most cases, structural changes and bradycardia regress with detraining, although approximately 20% of elite athletes have residual chamber enlargement, raising questions, in the absence of long-term data, about whether athlete’s heart is truly benign (1). Similarly, the association of myocardial fibrosis with endurance sports raises questions both about potential maladaptive cardiac remodeling in athletes and about an upper limit of healthy exercise in some individuals (2).
Prognosis references
1. Pelliccia A, Maron BJ, De Luca R, Di Paolo FM, Spataro A, Culasso F. Remodeling of left ventricular hypertrophy in elite athletes after long-term deconditioning. Circulation. 2002;105(8):944-949. doi:10.1161/hc0802.104534
2. Franklin BA, Thompson PD, Al-Zaiti SS, et al. Exercise-Related Acute Cardiovascular Events and Potential Deleterious Adaptations Following Long-Term Exercise Training: Placing the Risks Into Perspective-An Update: A Scientific Statement From the American Heart Association. Circulation. 2020;141(13):e705-e736. doi:10.1161/CIR.0000000000000749
Key Points
Intensive physical exercise increases left ventricular muscle mass, wall thickness, and chamber size, but systolic function and diastolic function remain normal.
Resting heart rate is slow and there may be a systolic ejection murmur at the left lower sternal border, and a third heart sound (S3); a fourth heart sound (S4) should be considered abnormal.
ECG shows bradycardia and signs of hypertrophy and sometimes other findings such as sinus arrhythmia, atrial or ventricular ectopy, and low-grade atrioventricular (AV) block.
Structural and ECG changes due to athlete's heart are asymptomatic; the presence of cardiovascular symptoms (eg, chest pain, dyspnea, palpitations) or third-degree AV block should prompt a search for an underlying cardiac disorder.







