


Hidradenitis suppurativa is a chronic, scarring, acnelike inflammatory process that occurs in the axillae, groin, inframammary and peri-anal regions. Diagnosis remains clinical and may be supported by biopsy. Treatment depends on the severity of disease (stage).
Hidradenitis suppurativa is a chronic inflammatory condition of the hair follicle and associated structures. In a large meta-analysis of several population-based, cross-sectional prevalence studies, the global prevalence of hidradenitis suppurativa was estimated to be 0.99% (95% CI, 0.67%–1.46%), with a female predominance (1). Younger adults, women, and Black people are disproportionately affected (2). There is a higher prevalence in patients with metabolic syndrome, inflammatory bowel disease (particularly Crohn disease), spondyloarthropathy (3), rheumatoid arthritis, and some variants of PAPA syndrome.
Complex interplays between genetic predisposition, lifestyle factors (eg, obesity, smoking), hormonal influences, and immune dysregulation (eg, upregulated Th1- and Th17-derived cytokines, downregulated regulatory T cells and Th22 cells) contribute to the development of disease (4). Bacterial dysbiosis (overgrowth of anaerobic, pathogenic bacteria and depletion of normal skin commensals) is thought to occur (5). Follicular inflammation and subsequent occlusion leads to rupture of the follicle and recurrent development of abscesses, sinus tracts, and scarring.
General references
1. Bouazzi D, Nielsen SM, Hagan PG, et al. Prevalence of Hidradenitis Suppurativa: A Meta-Analysis of Global Hidradenitis Suppurativa Atlas Studies. JAMA Dermatol. Published online August 27, 2025. doi:10.1001/jamadermatol.2025.2373
2. Midgette B, Garg A. Epidemiology of hidradenitis suppurativa and its comorbid conditions. J Am Acad Dermatol. 2024;91(6S):S3-S7. doi:10.1016/j.jaad.2024.09.013
3. Sabat R, Alavi A, Wolk K, et al. Hidradenitis suppurativa. Lancet. 2025;405(10476):420-438. doi:10.1016/S0140-6736(24)02475-9
4. Wolk K, Join-Lambert O, Sabat R. Aetiology and pathogenesis of hidradenitis suppurativa. Br J Dermatol. 2020;183(6):999-1010. doi:10.1111/bjd.19556
5. Soto-Moreno A, Haselgruber-de Francisco S, León-Pérez J, et al. The Microbiome in Hidradenitis Suppurativa Tunnels: A Systematic Review. Int J Dermatol. 2025;64(10):1802-1812. doi:10.1111/ijd.17892
Symptoms and Signs of Hidradenitis Suppurativa
Swollen, tender masses resembling cutaneous abscesses develop. These lesions are often sterile. Pain, pruritus, fluctuance, discharge, and sinus tract formation (sometimes called epithelialized tunnels) are characteristic in chronic cases. Bacterial infection may occur in deep abscesses and sinus tracts. In chronic axillary cases, coalescence of inflamed nodules causes palpable cordlike fibrotic bands. The condition may become debilitating because of pain and foul odor.
Rarely, longstanding, severe cases, particularly in the gluteal and perianal region can undergo malignant transformation (typically into a squamous cell carcinoma) (1). Such transformation is more frequently observed in males.
Symptoms and signs reference
1. Gierek M, Niemiec P, Szyluk K, et al. Hidradenitis suppurativa and squamous cell carcinoma: a systematic review of the literature. Postepy Dermatol Alergol. 2023;40(3):350-354. doi:10.5114/ada.2023.126563
Diagnosis of Hidradenitis Suppurativa
History and physical examination
Sometimes, biopsy

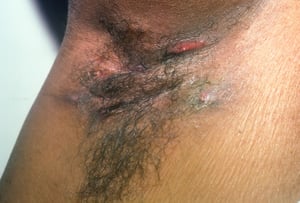
In this photo, multiple sinus tracts (shown as cordlike linear structures) suggest moderate hidradenitis suppurativa.
In this photo, multiple sinus tracts (shown as cordlike linear structures) suggest moderate hidradenitis suppurativa.
Photo courtesy of Karen McKoy, MD.

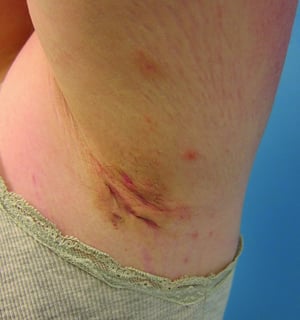
This patient has both scarring (with hyperpigmentation) and abscesses resulting from hydradenitis suppurativa.
This patient has both scarring (with hyperpigmentation) and abscesses resulting from hydradenitis suppurativa.
© Springer Science+Business Media

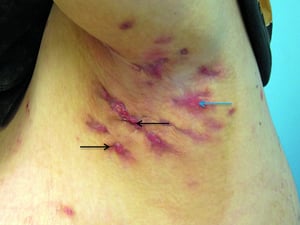
This patient has multiple chronically draining abscesses (blue arrow) and sinus tracts (black arrows).
This patient has multiple chronically draining abscesses (blue arrow) and sinus tracts (black arrows).
© Springer Science+Business Media
In this photo, multiple sinus tracts (shown as cordlike linear structures) suggest moderate hidradenitis suppurativa.
In this photo, multiple sinus tracts (shown as cordlike linear structures) suggest moderate hidradenitis suppurativa.
Photo courtesy of Karen McKoy, MD.
This patient has both scarring (with hyperpigmentation) and abscesses resulting from hydradenitis suppurativa.
This patient has both scarring (with hyperpigmentation) and abscesses resulting from hydradenitis suppurativa.
© Springer Science+Business Media
This patient has multiple chronically draining abscesses (blue arrow) and sinus tracts (black arrows).
This patient has multiple chronically draining abscesses (blue arrow) and sinus tracts (black arrows).
© Springer Science+Business Media
The diagnosis of hidradenitis suppurativa is primarily based on history and physical examination (1). Cultures should be taken from deep abscesses and sinus tracts in patients who have chronic disease, but often no pathogens will be found. The Hurley staging system describes the severity of disease (2):
Stage I: Abscess formation, single or multiple, without sinus tracts or scarring
Stage II: Single or multiple, widely separated, recurrent abscesses with sinus tract formation or scarring
Stage III: Diffuse or near diffuse involvement or multiple interconnected sinus tracts and abscesses across the entire area
Diagnosis references
1. Alikhan A, Sayed C, Alavi A, et al: North American clinical management guidelines for hidradenitis suppurativa: A publication from the United States and Canadian Hidradenitis Suppurativa Foundations: Part II: Topical, intralesional, and systemic medical management. J Am Acad Dermatol 81(1):91-101, 2019. doi: 10.1016/j.jaad.2019.02.068
2. Hurley HJ. Axillary hyperhidrosis, apocrine bromhidrosis, hidradenitis suppurativa, and familial benign pemphigus: surgical approach. In: Roenigk RK, Roenigk HH, eds. Dermatologic Surgery. Marcel Dekker; 1989:729–739
Treatment of Hidradenitis Suppurativa
Stage I: Topical clindamycin, intralesional glucocorticoids, and oral antibiotics
Stage II: Longer courses of oral antibiotics, antiandrogenic agents, and sometimes drainage, de-roofing, or punch debridement
Stage III: Biologic agents (eg, infliximab, adalimumab, secukinumab, bimekizumab) and often wide surgical excision and repair or grafting
Treatment goals in hidradenitis suppurativa are to prevent new lesions, reduce inflammation, and remove sinus tracts (1). Treatment approaches typically involve a combination of pharmacologic agents (eg, topical and oral antibiotics, oral antiandrogens, intralesional glucocorticoids, biologics) and surgical interventions.
For Hurley stage I disease, typical treatment includes topical 1% clindamycin solution 2 times a day, topical resorcinol 15% cream once a day, oral zinc gluconate (90 mg once a day), intralesional glucocorticoids (eg, 0.1 to 0.5 mL of a 5- to 10-mg/mL solution of triamcinolone acetonide once a month), and short (eg, 7- to 10-day) courses of oral antibiotics. Tetracycline, doxycycline, minocycline, or, less commonly, erythromycin are used until the lesions resolve. A typical regimen could include one topical treatment (eg, based on the patient's skin sensitivity) and an oral antibiotic; however, all treatments can be used in combination or alone. Skin affected by hidradenitis suppurativa can be washed with benzoyl peroxide washes; this includes the axillae, inframammary, groin, external genitalia, and the buttocks. Skin should be rinsed well to avoid peroxide-induced bleaching of the clothing.
For Hurley stage II disease, treatment is with a longer (eg, 2- to 3-month) course of the same oral antibiotics used to treat stage I disease; if response is incomplete, clindamycin and/or rifampin may be added to the regimen. Adding antiandrogen therapy (eg, with oral estrogen or combination oral contraceptives, spironolactone, cyproterone acetate [not available in the United States], finasteride, or combinations) may be helpful in women. Incision and drainage may reduce the pain of an abscess but are insufficient for disease control (unlike in common cutaneous abscesses). For acute inflammatory lesions that are not excessively deep, punch debridement (ie, excision with a 5- to 7-mm punch instrument followed by digital debridement and curettage or scrubbing) is preferable. Sinus tracts should be unroofed and debrided. Patients whose lesions are deeper should be evaluated by a plastic surgeon for consideration of excision and grafting.
For Hurley Stage III disease, medical and surgical therapy should be more aggressive (2). Evidence of efficacy in reducing inflammation is strongest for infliximab (3). Alternatively, adalimumab, secukinumab, or bimekizumab are also efficacious (4, 5, 6). Oral retinoids (isotretinoin for 4 to 6 months or acitretin for 9 to 12 months) have been effective in some patients (7). Wide surgical excision and repair or grafting of the affected areas is often necessary if the disease persists. Ablative laser therapy (CO2 or erbium:YAG) is an alternate surgical treatment (8). Laser hair removal has also been used with some success (9).
Recommended adjunctive measures for all patients with hidradenitis suppurativa include maintaining good skin hygiene, minimizing trauma, providing psychological support, and possibly avoiding high glycemic–load foods.
Treatment references
1. Alikhan A, Sayed C, Alavi A, et al. North American clinical management guidelines for hidradenitis suppurativa: A publication from the United States and Canadian Hidradenitis Suppurativa Foundations: Part II: Topical, intralesional, and systemic medical management. J Am Acad Dermatol. 2019;81(1):91-101. doi: 10.1016/j.jaad.2019.02.068
2. Calabrese L, Cartocci A, Rubegni P, et al. Efficacy and safety of biologics for hidradenitis suppurativa: A network meta-analysis of phase III trials. J Eur Acad Dermatol Venereol. 2026;40(4):637-645. doi:10.1111/jdv.20617
3. Shih T, Lee K, Grogan T, Deet al. Infliximab in hidradenitis suppurativa: A systematic review and meta-analysis. Dermatol Ther. 2022;35(9):e15691. doi: 10.1111/dth.15691
4. Kimball AB, Okun MM, Williams DA, et al. Two Phase 3 Trials of Adalimumab for Hidradenitis Suppurativa. N Engl J Med. 2016;375(5):422-434. doi: 10.1056/NEJMoa1504370
5. Kimball AB, Jemec GBE, Alavi A, et al. Secukinumab in moderate-to-severe hidradenitis suppurativa (SUNSHINE and SUNRISE): week 16 and week 52 results of two identical, multicentre, randomised, placebo-controlled, double-blind phase 3 trials. Lancet. 2023;401(10378):747-761. doi: 10.1016/S0140-6736(23)00022-3
6. Kimball AB, Jemec GBE, Sayed CJ, et al. Efficacy and safety of bimekizumab in patients with moderate-to-severe hidradenitis suppurativa (BE HEARD I and BE HEARD II): two 48-week, randomised, double-blind, placebo-controlled, multicentre phase 3 trials. Lancet. 2024;403(10443):2504-2519. doi:10.1016/S0140-6736(24)00101-6
7. Matusiak L, Bieniek A, Szepietowski JC. Acitretin treatment for hidradenitis suppurativa: a prospective series of 17 patients. Br J Dermatol. 2014;171(1):170-174. doi: 10.1111/bjd.12884
8. Tierney E, Mahmoud BH, Hexsel C, et al. Randomized control trial for the treatment of hidradenitis suppurativa with a neodymium-doped yttrium aluminium garnet laser. Dermatologic Surgery. 2009;35(8):1188-1198. doi: 10.1111/j.1524-4725.2009.01214.x
9. Xu LY, Wright DR, Mahmoud BH, et al. Histopathologic study of hidradenitis suppurativa following long-pulsed 1064-nm Nd:YAG laser treatment. Arch Dermatol. 2011;147(1):21-28. doi: 10.1001/archdermatol.2010.245
Key Points
Lesions are usually sterile except for deep abscesses and sinus tracts in chronic disease.
Hidradenitis suppurativa can be disabling.
The diagnosis and treatment of hidradenitis suppurativa are based on the Hurley staging system.
Adjunctive measures include maintaining good skin hygiene, minimizing trauma, providing psychological support, and possibly avoiding a high glycemic-load diet.
Drug Information for the Topic







