


Stevens-Johnson syndrome and toxic epidermal necrolysis are severe cutaneous hypersensitivity reactions. Medications, especially sulfonamides, antiseizure medications, and antibiotics, are the most common causes. Macules rapidly spread and coalesce, leading to epidermal blistering, necrosis, and sloughing. Diagnosis is usually obvious by appearance of initial lesions and clinical syndrome. Treatment is supportive care; cyclosporine, plasmapheresis or IV immune globulin, early glucocorticoid therapy, and tumor necrosis factor inhibitors have been used.
Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN) are clinically similar except for their distribution. Toxic epidermal necrolysis is sometimes called Lyell syndrome. By one commonly accepted definition, changes affect (1):
< 10% of body surface area in SJS
10 to 30% of body surface area in SJS/TEN overlap
> 30% of body surface area in TEN
The disorders affect between 2 and 9 people/million (2). The incidence, severity, or both of these disorders may be higher in recipients of bone marrow transplants, in patients with HIV who have Pneumocystis jirovecii infection, in patients with systemic lupus erythematosus, and in patients with other chronic systemic rheumatic diseases.
General references
1. Lerch M, Mainetti C, Terziroli Beretta-Piccoli B, et al. Current Perspectives on Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis. Clin Rev Allergy Immunol. 2018;54(1):147-176. doi:10.1007/s12016-017-8654-z
2. Hsu DY, Brieva J, Silverberg NB, Silverberg JI. Morbidity and Mortality of Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis in United States Adults. J Invest Dermatol. 2016;136(7):1387-1397. doi:10.1016/j.jid.2016.03.023
Etiology of SJS and TEN
Medications precipitate most cases of SJS and TEN in adults. The most common medications precipitating SJS and TEN include:
Sulfonamide antibiotics (eg, sulfasalazine)
Other antibiotics (eg, aminopenicillins [usually ampicillin or amoxicillin], fluoroquinolones, cephalosporins)
Antiseizure medications (eg, phenytoin, carbamazepine, phenobarbital, valproic acid and its derivatives, lamotrigine)
Nonsteroidal anti-inflammatory drugs (eg, piroxicam, meloxicam)
Antiretroviral medications (eg, nevirapine)
Miscellaneous individual medications (eg, allopurinol, chlormezanone)
Immune checkpoint inhibitors (1)
Cases that are not caused by medications are attributed to:
Infection (mostly with Mycoplasma pneumoniae)
Vaccination
In children with Stevens-Johnson syndrome, an infection is the most likely cause, and most of those are related to M. pneumoniae.
Rarely, a cause cannot be identified.
Etiology reference
1. Zhu J, Chen G, He Z, et al. Stevens-Johnson syndrome/toxic epidermal necrolysis in patients treated with immune checkpoint inhibitors: A safety analysis of clinical trials and FDA pharmacovigilance database. EClinicalMedicine. 2021;37:100951. Published 2021 Jun 10. doi:10.1016/j.eclinm.2021.100951
Pathophysiology of SJS and TEN
The exact underlying mechanism by which Stevens-Johnson syndrome and toxic epidermal necrolysis occur is poorly characterized. One hypothesis is that altered drug metabolism (eg, failure to clear reactive drug metabolites) in some patients triggers a T-cell–mediated cytotoxic reaction to drug antigens in keratinocytes. CD8+ T cells have been identified as important mediators of blister formation. Findings suggest that granulysin released from cytotoxic T cells and natural killer cells might play a role in keratinocyte death; granulysin concentration in blister fluid correlates with severity of disease. Interleukin-15 has also been found to be increased in patients with SJS/TEN and has been found to increase granulysin production.
Another hypothesis is that interactions between Fas (a cell-surface receptor that induces apoptosis) and its ligand, particularly a soluble form of Fas ligand released from mononuclear cells, lead to cell death and blister formation.
A genetic predisposition for SJS/TEN is well-established, with strong associations between specific HLA alleles and drug-induced severe cutaneous adverse reactions. Testing for the presence of certain HLA allelic variants before the administration of certain medications may be considered, particularly in certain Northern European or Asian populations (eg, HLA-B*58:01 for allopurinol, HLA-A*31:01, HLA-B*15:02 for carbamazepine) (1).
Pathophysiology reference
1. Duong TA, Valeyrie-Allanore L, Wolkenstein P, et al. Severe cutaneous adverse reactions to drugs. Lancet. 2017;390(10106):1996-2011. doi:10.1016/S0140-6736(16)30378-6
Symptoms and Signs of SJS and TEN
Within 1 to 3 weeks after the start of the offending medication, patients develop a prodrome of malaise, fever, headache, cough, and keratoconjunctivitis (1). Macules, often in a target configuration (bull's eye configuration), then appear suddenly, usually on the face, neck, and upper trunk. These macules simultaneously appear elsewhere on the body, coalesce into large flaccid bullae, and slough over a period of 1 to 3 days (1). Nails and eyebrows may be lost along with epithelium. The palms and soles may be involved. Skin, mucosal, and eye pain are common. In some cases, diffuse erythema is the first skin abnormality of TEN.

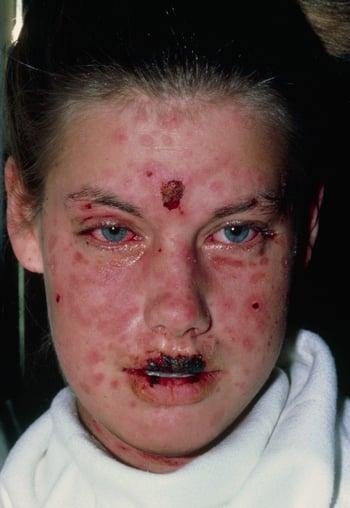
This photo shows an erythematous rash and blisters on the skin and on the mucosa of the eyes and mouth in this patient with SJS.


This photo shows numerous erythematous to dusky macules and papules, some coalescing, with visible areas of epidermal detachment and denudation. Mucosal involvement includes erosions and ulceration of the lips and eyes.
DR M.A. ANSARY/SCIENCE PHOTO LIBRARY


This photo shows extensive necrosis and splitting and sloughing of the epidermis from the dermis secondary to drug-induced toxic epidermal necrolysis on the torso of a 60 year old woman. It is a rare but life-threatening skin condition.
PDC/SCIENCE PHOTO LIBRARY
In severe cases of TEN, large sheets of epithelium slide off the entire body at pressure points (ie, positive Nikolsky sign), exposing weepy, painful, and erythematous skin. Painful oral crusts and erosions, keratoconjunctivitis, and genital problems (eg, urethritis, phimosis, vaginal synechiae) accompany skin sloughing in most cases. Bronchial epithelium may also slough, causing cough, dyspnea, pneumonia, pulmonary edema, and hypoxemia. Glomerulonephritis and hepatitis may develop.
Symptoms and signs reference
1. Mawson AR, Eriator I, Karre S. Stevens-Johnson syndrome and toxic epidermal necrolysis (SJS/TEN): could retinoids play a causative role?. Med Sci Monit. 2015;21:133-143. Published 2015 Jan 12. doi:10.12659/MSM.891043
Diagnosis of SJS and TEN
Primarily history and physical examination
Often skin biopsy
The diagnosis is usually clinically evident from the appearance of lesions and rapid progression of symptoms. Histologic examination of sloughed skin shows necrotic epithelium, a distinguishing feature.
Differential diagnosis in Stevens-Johnson syndrome (SJS) and early toxic epidermal necrolysis (TEN) includes erythema multiforme, viral exanthems, and other drug rashes; SJS/TEN can usually be differentiated clinically as the disorder evolves and is characterized by significant pain and skin sloughing. In later stages of TEN, differential diagnosis includes the following:
Toxic shock syndrome (usually has more prominent multiorgan involvement and different cutaneous manifestations, such as macular rash on palms and soles that evolves to desquamation over about 2 weeks)
Exfoliative erythroderma (usually spares mucous membranes and is not as painful)
Paraneoplastic pemphigus (sometimes with different mucocutaneous findings or in patients with evidence of cancer)
In children, TEN is less common and must be distinguished from staphylococcal scalded skin syndrome. Characteristics of staphylococcal scalded skin syndrome usually include sparing of mucous membranes, absence of risk factors for TEN (eg, medication history), and clinical suspicion of staphylococcal infection.
(See also table .)
Treatment of SJS and TEN
Supportive care
Cyclosporine or tumor necrosis factor (TNF) inhibitors
Possibly other agents (eg, glucocorticoids, plasmapheresis, IV immune globulin [IVIG])
The treatment of Stevens-Johnson syndrome and toxic epidermal necrolysis (SJS/TEN) involves early recognition and inpatient management with immediate discontinuation of the causative drug, and intensive supportive care (including fluids, wound care, infection control, nutritional, and ophthalmologic management). The role of systemic immunomodulatory therapy is uncertain and supported by limited evidence. Cyclosporine and some TNF inhibitors (eg, etanercept) may decrease mortality (1). Other immunomodulatory therapies that have been used include intravenous immunoglobulin (IVIG), glucocorticoids, and plasmapheresis. Outcomes are optimal when SJS/TEN is recognized early and treated in an inpatient dermatologic or intensive care unit setting; treatment in a burn unit may be needed for severe disease (2). Ophthalmology consultation and specialized eye care are mandatory for patients with ocular involvement.
Medications suspected to have triggered SJS/TEN should be stopped immediately. Patients are isolated to minimize exposure to infection and are given fluids, electrolytes, blood products, and nutritional supplements as needed. Skin care includes prompt treatment of secondary bacterial infections and daily wound care as for severe burns. Prophylactic systemic antibiotics are not routinely recommended in the absence of clinical evidence of infection, but can be given when bacterial infection or sepsis is suspected.
Pharmacotherapy of SJS/TEN is controversial. Immunomodulatory agents may be considered (1). Cyclosporine (3 to 5 mg/kg orally once/day) inhibits CD8 T cells and has been shown to decrease the duration of active disease (eg, by 2 to 3 days in some instances) and possibly decrease mortality (3). Limited evidence supports the use of the TNF. inhibitors infliximab and etanercept in reducing inflammation; etanercept can additionally reduce disease-specific mortality. The use of systemic glucocorticoids remains controversial. Many experts thought systemic glucocorticoids increased mortality because of increased rates of infection and the risk of masking sepsis. However, some reports have shown improved outcomes with early glucocorticoid therapy (4). Early IVIG (typically 1 to 2 g/kg total, administered over 2 to 5 days) blocks Fas-receptor and ligand (Fas-FasL) interaction through antibodies that target Fas (CD95). However, despite some remarkable initial results using high-dose IVIG for TEN, further clinical trials involving small cohorts have reported conflicting results, and a retrospective analysis has suggested no improvement or even higher than expected mortality (5) JAK inhibitors are an emerging treatment option for TEN; early clinical experience suggests benefit, although evidence remains limited (6).
Plasmapheresis can remove reactive drug metabolites or antibodies and can be considered.
Treatment references
1. Gladman J, Kloczko E. Cochrane corner: Systemic interventions for treatment of Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and SJS/TEN overlap syndrome. Clin Exp Allergy. 2022;52(11):1244-1246. doi:10.1111/cea.14211
2. Seminario-Vidal L, Kroshinsky D, Malachowski SJ, et al. Society of Dermatology Hospitalists supportive care guidelines for the management of Stevens-Johnson syndrome/toxic epidermal necrolysis in adults. J Am Acad Dermatol. 2020;82(6):1553-1567. doi:10.1016/j.jaad.2020.02.066
3. Ng QX, De Deyn MLZQ, Venkatanarayanan N, Ho CYX, Yeo WS. A meta-analysis of cyclosporine treatment for Stevens-Johnson syndrome/toxic epidermal necrolysis. J Inflamm Res. 2018;11:135-142. Published 2018 Mar 28. doi:10.2147/JIR.S160964
4. Zimmermann S, Sekula P, Venhoff M, et al. Systemic Immunomodulating Therapies for Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis: A Systematic Review and Meta-analysis. JAMA Dermatol. 2017;153(6):514-522. doi:10.1001/jamadermatol.2016.5668
5. Kirchhof MG, Miliszewski MA, Sikora S, et al. Retrospective review of Stevens-Johnson syndrome/toxic epidermal necrolysis treatment comparing intravenous immunoglobulin with cyclosporine. J Am Acad Dermatol. 2014;71(5):941–947. doi:10.1016/j.jaad.2014.07.016
6. Nordmann TM, Anderton H, Hasegawa A, et al. Spatial proteomics identifies JAKi as treatment for a lethal skin disease. Nature. 2024;635(8040):1001-1009. doi:10.1038/s41586-024-08061-0
Prognosis for SJS and TEN
Severe toxic epidermal necrolysis is similar to extensive burns; patients are acutely ill, may be unable to eat or open their eyes, and suffer massive fluid and electrolyte losses. They are at high risk of infection, multiorgan failure, and death.
Mortality risk generally depends on age, clinical severity of disease, and extent of body surface involvement (eg, higher in TEN than SJS). Mortality can be as high as 25 to 35% in adults but is usually lower in children and with early treatment (1).
With early therapy, survival rates for TEN approach 90%. The systematically scores 7 independent risk factors within the first 24 hours of presentation to the hospital to determine the mortality rate for a particular patient.
In survivors, long-term physical and psychological sequelae can develop. Observational data have shown significantly higher rates of cutaneous, ocular, oral mucosal and psychological comorbidities (2).
Severity-of-Illness Score for Toxic Epidermal Necrolysis (SCORTEN)
Risk Factor* | Score | |
|---|---|---|
0 | 1 | |
Age | < 40 years | ≥ 40 years |
Associated cancer | No | Yes |
Heart rate (beats/minute) | < 120 | ≥ 120 |
Serum blood urea nitrogen | ≤ 28 mg/dL (10 mmol/L) | > 28 mg/dL (10 mmol/L) |
Detached or compromised body surface | < 10% | ≥ 10% |
Serum bicarbonate | ≥ 20 mEq/L (≥ 20 mmol/L) | < 20 mEq/L (< 20 mmol/L) |
Serum glucose | ≤ 250 mg/dL (≤ 13.88 mmol/L) | > 250 mg/dL (> 13.88 mmol/L) |
* More risk factors indicate a higher score and a higher mortality rate (%) as follows:
| ||
CI = confidence interval. | ||
Data from Bastuji-Garin S, Fouchard N, Bertocchi M, et al: SCORTEN: A severity-of-illness score for toxic epidermal necrolysis. J Invest Dermatol. 2000;115:149–153. doi: 10.1046/j.1523-1747.2000.00061.x | ||
Prognosis references
1. Del Pozzo-Magaña BR, Lazo-Langner A. Stevens-Johnson Syndrome and Toxic Epidermal Necrolysis in Children: A Literature Review of Current Treatments. EMJ Dermatol. 2016;4[1]:83-89. doi:10.33590/emjdermatol/10314211
2. Hoffman M, Chansky PB, Bashyam AR, et al. Long-term Physical and Psychological Outcomes of Stevens-Johnson Syndrome/Toxic Epidermal Necrolysis. JAMA Dermatol. 2021;157(6):712-715. doi:10.1001/jamadermatol.2021.1136
Key Points
Drugs cause most cases of Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN), but infection, vaccination, and graft-vs-host disease are also potential causes.
Confirm the diagnosis by biopsy (showing necrotic epithelium) if clinical characteristics (eg, target lesions progressing to bullae, ocular and mucous membrane involvement, positive Nikolsky sign, desquamation in sheets) are inconclusive.
Early treatment decreases the often high mortality rate.
Except for mild cases, treat SJS/TEN in a burn unit and with intensive supportive care.
Consult ophthalmology if there is eye involvement.
Consider cyclosporine, etanercept, or other immunomodulatory therapies, and possibly plasmapheresis for severe cases.
Drug Information for the Topic







