


Astrocytomas are tumors in the central nervous system (the central nervous system is made up of the brain and spinal cord) that develop during childhood. These tumors develop from star-shaped cells called astrocytes that help nerve cells in the brain or spinal cord function. They may be cancerous (malignant) or noncancerous (benign).
Children may have difficulty walking, weakness, vision changes, vomiting, and headaches.
Diagnosis usually involves an imaging test of the brain, spine, or both and a biopsy.
Treatment options include surgery, chemotherapy, and sometimes radiation therapy.
The prognosis typically depends on the grade of the tumor, specific genetic mutations or characteristics, and other factors.
Astrocytomas are the most common brain and spinal cord tumors in children, accounting for about 40% of cases. These tumors are usually diagnosed in children under 9 years old. These tumors can occur anywhere in the brain or spinal cord but are common in the cerebellum (the area near the base of the brain that coordinates the body’s movements).

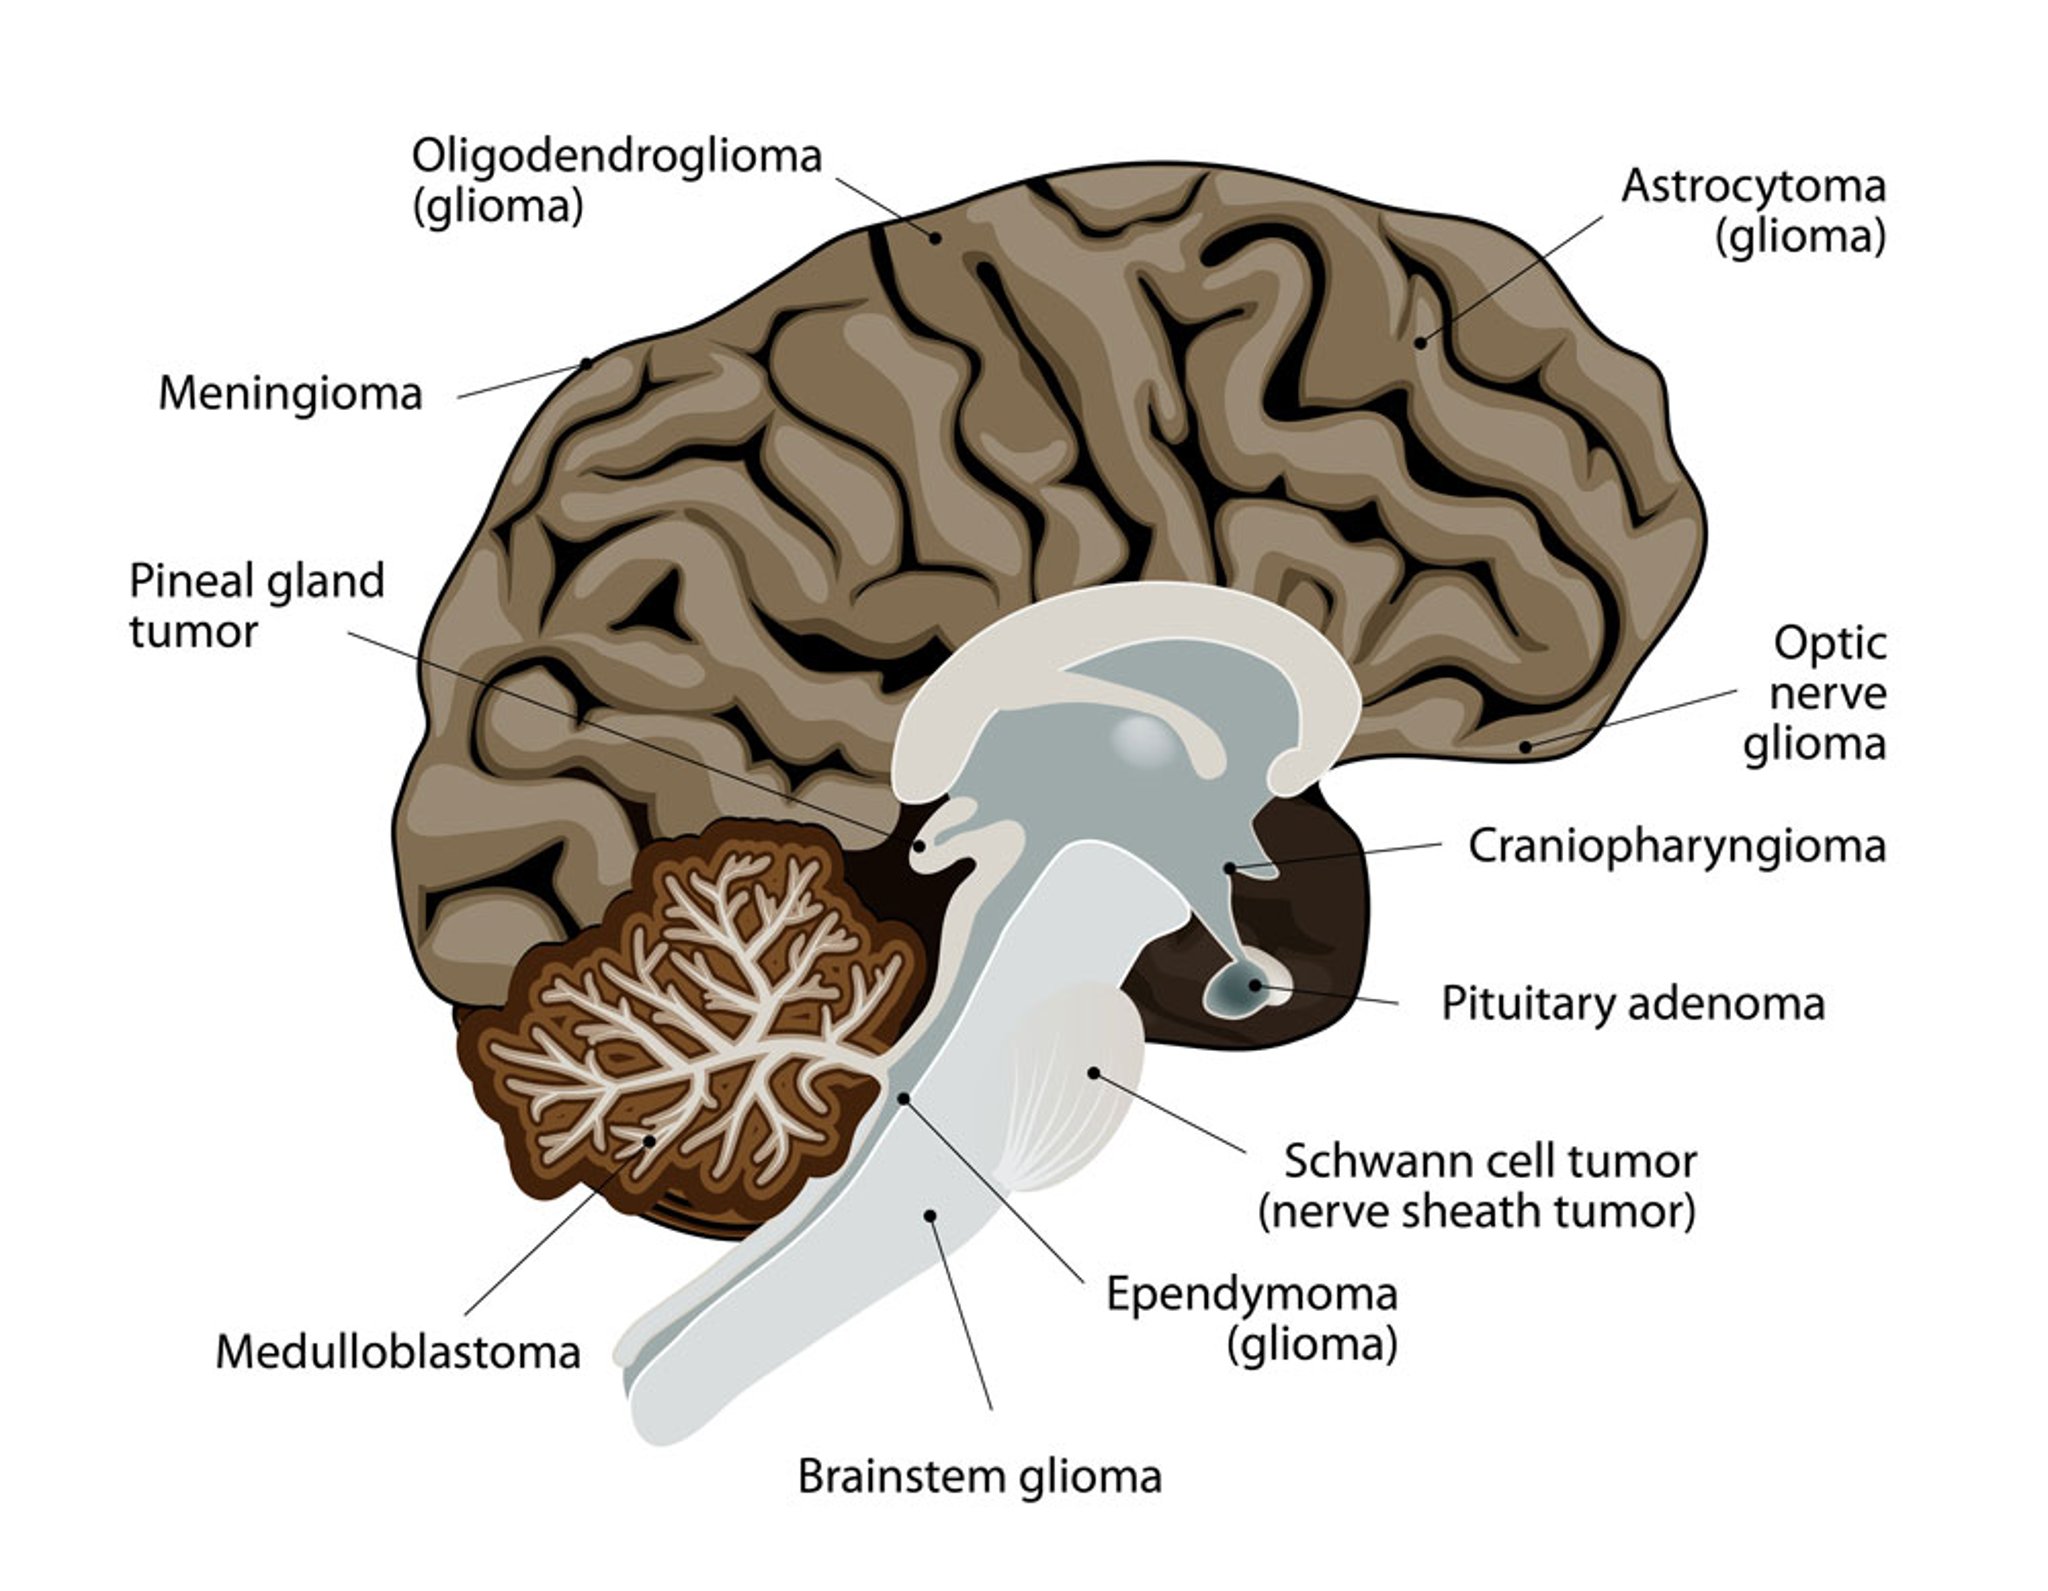
Starting from the top right label:
Astrocytoma (glioma)
Optic nerve glioma
Craniopharyngioma
Pituitary adenoma
Schwann cell tumor (nerve sheath tumor)
Ependymoma (glioma)
Brain stem glioma
Medulloblastoma
Pineal gland tumor
Meningioma
Oligodendroglioma (glioma)
designua/stock.adobe.com
Astrocytomas are a type of brain tumor called a glioma.
Symptoms of Astrocytomas in Children
Astrocytomas in the brain cause pressure within the skull to increase, which causes headaches (often when children first awaken), vomiting, and listlessness. Children become weak and may lose their coordination and have difficulty walking. Vision may be blurred or lost, and the eyes may bulge. The child may have nystagmus, in which the eyes involuntarily jerk in one direction, then drift back.


Astrocytomas in the spinal cord may cause back pain, difficulty walking, numbness, changes in bowel or bladder function, and muscle weakness.
Diagnosis of Astrocytomas in Children
Magnetic resonance imaging
Biopsy
Doctors typically do a magnetic resonance imaging (MRI) scan of the brain, spine, or both to detect the tumor. Before the MRI scan is done, doctors inject a contrast agent into the child's vein (intravenously). Contrast agents are substances that make organs and other structures clearer to see on imaging tests. If MRI is unavailable, doctors do another imaging test called computed tomography (CT), but it provides less detail.
Then doctors usually take a sample of tissue from the tumor and examine it under a microscope (biopsy) because treatment is based on the type of tumor and on how abnormal the tumor cells look (the tumor’s grade). They may also do genetic tests on the sample to determine whether the tumor has a mutation in a specific gene, such as the BRAF or IDH gene. The results of these tests help doctors determine treatment.
After doctors examine the tumor sample, they assign it a grade. Astrocytomas are typically classified as low grade (for example, pilocytic astrocytoma) or high grade (for example, anaplastic astrocytoma or glioblastoma). Grades 1 and 2 tumors are considered low grade with better outcomes, and grades 3 and 4 tumors are considered high grade with poorer outcomes.
Treatment of Astrocytomas in Children
Surgery (if possible)
Sometimes chemotherapy
(See also Cancer Treatment Principles.)
Most low-grade astrocytomas are surgically removed. If the astrocytoma is completely removed, children may not need any other treatment. However, sometimes surgery is not possible.
Chemotherapy is sometimes given, especially to children who have a tumor that cannot be removed surgically or that progresses or returns after surgery.
Radiation therapy is rarely used to treat children who have low-grade astrocytomas, and doctors avoid using it if possible because it can interfere with physical growth and brain development (including later learning, thinking, reasoning, and understanding), as well as lead to other cancers and blood vessel problems.
Targeted therapy may be given to children whose tumor has a mutation of a specific gene such as the BRAF gene. In targeted therapy, medications attack specific parts of cells that are present only in the cancer cells that have the specific gene mutation. For example, tovorafenib and dabrafenib are medications that target cells with a BRAF gene alteration.
Most low-grade astrocytomas can be treated successfully, and children are long-term survivors.
High-grade astrocytomas are treated with a combination of surgery (if possible), radiation therapy, and chemotherapy (see Combination Cancer Therapy). The most commonly used chemotherapy medications are temozolomide and lomustine.
The outlook is worse for children with a high-grade astrocytoma, and overall survival is only 10 to 30% 2 years after treatment.
More Information
The following English-language resource may be useful. Please note that The Manual is not responsible for the content of this resource.
American Cancer Society: How to Cope if Your Child Has Cancer
Drug Information for the Topic




