


Percutaneous cannulation of the subclavian vein uses anatomic landmarks to guide venipuncture and a guidewire (Seldinger technique) to thread a central venous catheter through the subclavian vein and into the superior vena cava. Two approaches (infraclavicular and supraclavicular) are used; the infraclavicular approach is described here.
Subclavian vein cannulation is often preferred in intensive care unit (ICU) settings when the goal is to reduce infection (1). Normal subclavian anatomy is relatively consistent, which supports a landmark approach. However, the apical pleura lies close to the needle path, and complications from an errant puncture (soft-tissue bleeding, hematoma, hemothorax, and pneumothorax) can be more serious than at other central venous catheter (CVC) sites because the venipuncture site is shielded by the overlying clavicle and cannot be monitored or compressed.
Real-time ultrasound guidance has been shown to reduce procedural complications of subclavian vein catheterization and to improve overall and first-attempt success rates while reducing the number of needle passes and access time (2). It is recommended for clinicians performing subclavian central venous access by major professional societies, including the American Society of Anesthesiologists, the Society of Hospital Medicine, and consensus guidelines on bedside ultrasonography in critically ill patients (3, 4, 5). The supporting evidence for the subclavian site is of lower certainty than for the internal jugular vein, with results equivocal for some individual complications such as arterial puncture and hematoma, and adoption in routine clinical practice remains variable despite these recommendations.
(See also Vascular Access, Central Venous Catheterization, and How To Do Subclavian Vein Cannulation, Ultrasound-Guided.)
Indications for Infraclavicular Subclavian Vein Cannulation
Secure or long-term venous access that is not available using other sites
Inability to obtain peripheral venous access or intraosseous infusion
IV infusion of fluids and medications for patients in cardiac arrest
IV infusion of medications that may be irritating to veins when administered peripherally (eg, high-concentration fluids, chemotherapy, vasopressors, parenteral nutrition)
IV infusion of high flows or large fluid volumes beyond what is possible using peripheral venous catheters
Hemodynamic monitoring (eg, central venous pressure, central venous oxyhemoglobin saturation, cardiac pressures via pulmonary artery catheters)
Transvenous cardiac pacing or pulmonary arterial monitoring (Swan-Ganz catheter)†
* The subclavian vein may be less preferred for stiff catheters (because of difficulty achieving the sharp turn into the superior vena cava) or large-bore hemodialysis catheters (which can cause venous stenosis that renders the ipsilateral arm unsuitable for arteriovenous shunt placement).
† For transvenous cardiac pacing and pulmonary arterial monitoring, a right internal jugular cannulation or a left subclavian vein cannulation typically is preferred.
A subclavian CVC is often favored for long-term central venous access in patients who are not confined to bed (eg, ambulatory patients needing parenteral nutrition, antibiotics, chemotherapy).
Contraindications for Infraclavicular Subclavian Vein Cannulation
Absolute contraindications:
Subclavian vein thrombosis
Fracture of the clavicle or proximal ribs
Local infection at the insertion site
Antibiotic-impregnated catheter in a patient with an allergy to the specific antibiotic
Relative contraindications:
Unilateral lung disease: Cannulate ipsilaterally (same side as diseased lung).
Local anatomic distortion, traumatic or congenital, without pneumothorax: Cannulate contralaterally.
Cardiac pacemaker/defibrillator: Do not cannulate the vein being used for the pacemaker leads.
Obesity: Because the axillary vein lies deep and the brachial plexus is nearby, cannulate the axillary vein only in patients with adequate ultrasound images.
Young children and infants: Subclavian vein cannulation is the least preferred CVC for young children and infants because of unfavorable anatomy, including the vein’s close proximity to the pleura and subclavian artery.
Coagulopathy, thrombocytopenia, anticoagulant/antiplatelet medications: See note.*
Malignant superior vena cava syndrome: Avoid superior vena cava cannulation; if absolutely necessary, use imaging guidance.
Severe cardiorespiratory insufficiency or increased intracranial or intraocular pressure: These patients will be compromised by Trendelenburg (head down) positioning.
History of prior catheterization of the subclavian vein: Prior catheterization may have resulted in scar tissue formation making catheter placement more difficult.
Uncooperative patient: Sedate if necessary.
Left bundle branch block: A guidewire or catheter in the right ventricle can induce complete heart block.
* Although percutaneous central venous cannulation carries a low risk of causing bleeding (6), anticoagulant medications (eg, for atrial fibrillation) increase the risk with central venous cannulation, but this risk must be balanced against the increased risk of thrombosis (eg, stroke) if anticoagulation is reversed (7). Discuss any contemplated reversal with the clinician managing the patient's anticoagulation and then with the patient. A femoral line may also be chosen as it is a more easily compressible site.
Complications for Infraclavicular Subclavian Vein Cannulation
(See also Complications of central venous catheterization.)
Potential complications include:
Pneumothorax (increased risk because apical pleura [especially on the left side] is close to needle insertion path)
Arterial puncture
Hematoma (increased risk because clavicle impedes application of external pressure to stop subclavian arterial or venous bleeding)
Damage to the vein
Catheter misplacement* (eg, internal jugular vein or thoracic duct)
Arrhythmias or atrial perforation, typically caused by the guidewire or catheter
Nerve damage
Infection
Thrombosis (due to the catheter itself)
* Rare complications due to catheter misplacement include arterial catheterization, hydrothorax, hydromediastinum, and damage to the tricuspid valve.
Guidewire or catheter embolism also rarely occurs (8).
To reduce the risk of venous thrombosis and blood stream infection associated with the central line, CVCs should be removed as soon as they are no longer needed (9).
Equipment for Infraclavicular Subclavian Vein Cannulation
Sterile procedure, barrier protection
Antiseptic solution (eg, chlorhexidine-alcohol, chlorhexidine, povidone-iodine, alcohol)
Large sterile drapes, towels
Sterile hats, masks, gowns, gloves
Face shields
Seldinger (catheter-over-guidewire) technique
Cardiac monitor
Local anesthetic (eg, 1% lidocaine without epinephrine, approximately 5 mL)
Small anesthetic needle (eg, 25 to 27 gauge, 3 cm [approximately 1 inch] long)
Large anesthetic/finder* needle (22 gauge, 4 cm [approximately 1.5 inches] long)
Introducer needle (eg, thin-walled, 18 or 16 gauge, with internally beveled hub, 6 cm [approximately 2.5 inches] long)
3- and 5-mL syringes (use slip-tip syringes for the finder and introducer needles)
Guidewire, J-tipped
Scalpel (#11 blade)
Dilator
Central venous catheter (adult: 8 French or larger, single- or multi-lumen as clinically indicated, minimum length for subclavian catheter is 20 cm [approximately 8 inches] for right side and 24 cm [approximately 9.5 inches] for left side)
Sterile gauze (eg, 10 × 10 cm [4 × 4 inch] squares)
Sterile saline for flushing catheter port or ports
Nonabsorbable nylon or silk suture (eg, 3-0 or 4-0)
Chlorhexidine patch
Transparent occlusive dressing
* A finder needle is a thinner needle used for locating the vein before inserting the introducer needle. It is optionally used for subclavian vein cannulation that is not guided by ultrasound.
Having 1 or 2 assistants is helpful.
Additional Considerations for Infraclavicular Subclavian Vein Cannulation
Cannulation attempts sometimes fail. Do not exceed 2 or 3 attempts, which increases the risk of complications, particularly with a landmark-based technique (3, 10, 11). Use new equipment with each attempt (ie, do not re-use needles, catheters, or other equipment because they may have become blocked with tissue or blood).
During cardiopulmonary arrest, or even low blood pressure and hypoxia, arterial blood may be dark and not pulsatile and may be mistaken for venous blood.
If the subclavian artery is errantly cannulated by either the tissue dilator or the CVC, leave the dilator or catheter in place and obtain surgical consultation for possible surgical removal.
Relevant Anatomy for Infraclavicular Subclavian Vein Cannulation
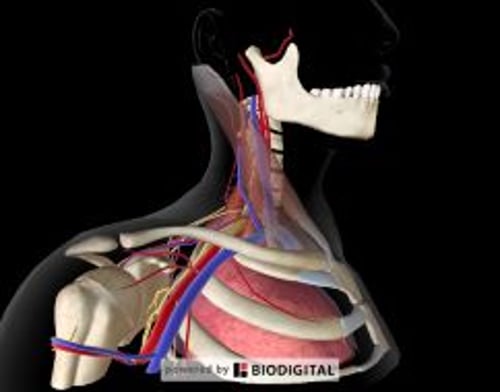
Superiorly overlying the first rib, in sequence from anterior to posterior, are the clavicle, subclavian vein, anterior scalene muscle, and subclavian artery.
Just medial to the junction of the medial and middle thirds of the clavicle, the subclavian vein is attached by fibrous tissue to both the first rib and the clavicle, stabilizing its position and diameter. At this site, the size of the subclavian vein is only slightly affected by respiration, the Trendelenburg position, or the Valsalva maneuver. This region of the vein is the intended target of subclavian venipuncture using the infraclavicular approach.
The infraclavicular approach is most common, and one of two skin insertion sites is used: either 1 to 2 cm inferior to the clavicle at the junction of its medial and middle thirds, or just inferior to the clavicle at its midpoint. Needles are advanced medially along a coronal (frontal) plane—skirting beneath the clavicle—toward the sternal notch. At the first site, the underlying first rib offers protection against pneumothorax. At the second site (clavicular midpoint), less effort is needed to maintain the shallow angle of insertion that keeps the needle in the coronal plane.
Right subclavian cannulation, versus left, is sometimes preferred because it avoids the thoracic duct and because the right pleural apex is lower than the left. Left cannulation is sometimes preferred (especially for pulmonary arterial catheterization) because it affords a direct, less angular path to the superior vena cava, with less chance of misdirected catheterization of the internal jugular vein.
Positioning for Infraclavicular Subclavian Vein Cannulation
Raise the bed to a comfortable height for you (ie, so you may stand straight while doing the procedure).
Place the patient supine or in Trendelenburg position (bed tilted with the head down 10 to 20°) to prevent air embolism.
Keep the patient's arm adducted and the head neutral.
Stand at the side of the bed.
Step-by-Step Description of Infraclavicular Subclavian Vein Cannulation
Do a preliminary inspection (nonsterile) to identify the sternal notch, the posterior bend of the clavicle, the junction of the medial and middle thirds of the clavicle, and the midpoint of the clavicle.
Attach the cardiac monitor to the patient and turn it on.
Prepare the equipment
Place sterile equipment on sterilely covered equipment trays.
Use appropriate personal protective equipment.
Draw the local anesthetic into a syringe.
Optional: Attach a finder needle to a 5-mL syringe with 1 to 2 mL of sterile saline in it.
Attach the introducer needle to a 5-mL syringe with 1 to 2 mL of sterile saline in it. Align the bevel of the needle with the volume markings on the syringe.
Pre-flush all lines of the CVC with 3 to 5 mL of sterile saline and then close the ports with caps or syringes.
When flushing a central line, use a 10-mL syringe (or one of equal or greater diameter) and do not push too hard to avoid rupturing the line.
Prepare the sterile field
Swab a broad area of skin with antiseptic solution, encompassing the entire clavicular area, as well as the side of the neck and anterior chest to below the ipsilateral nipple. Creating this broad sterile area permits immediately switching to internal jugular cannulation, should this subclavian vein cannulation fail.
Allow the antiseptic solution to dry for at least 1 to 2 minutes.
Put on sterile mask, hat, gown, and gloves.
Place sterile towels around the site.
Place large sterile drapes (eg, a full-body drape) to establish a large sterile field.
Establish the needle insertion path (subclavian vein, infraclavicular approach)
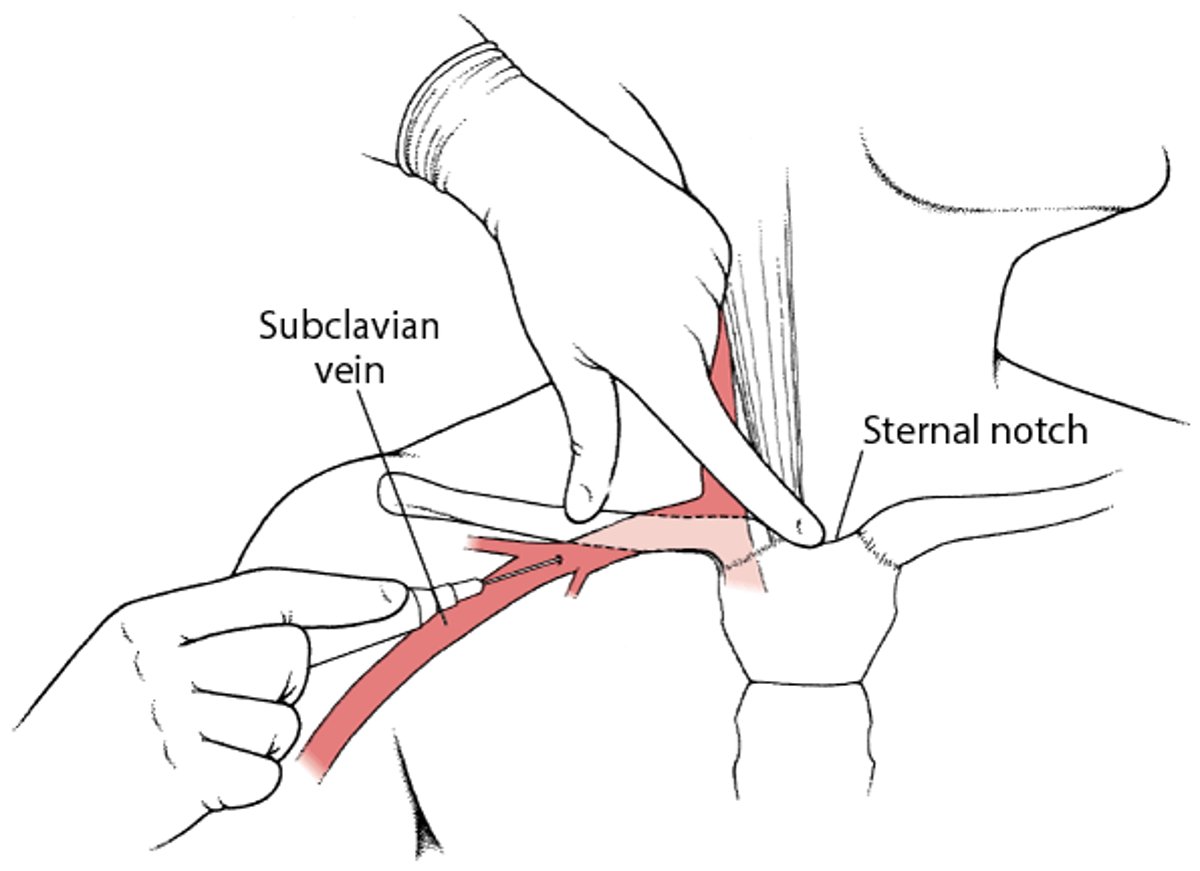
Place the tip of your index finger of the hand closest to the head of the bed on the sternal notch and your thumb at the midpoint of the clavicle.
The needle insertion path: Insert procedural needles (local anesthetic, finder, and introducer needles) immediately inferior to the clavicular midpoint (or 1 to 2 cm inferior to the junction of the medial and middle thirds of the clavicle), at a shallow angle into the skin, and—skirting the underside of the clavicle—aim toward the sternal notch.
You likely will need to push downward on the skin lateral to the needle insertion point to maintain the required, nearly horizontal, orientation of the syringe and needle.
Anesthetize the cannulation site
Place a wheal of anesthetic at the needle entry site and then inject anesthetic into the skin and soft tissues along the anticipated needle insertion path. Place extra anesthetic in the highly pain-sensitive periosteum on the underside of the clavicle. Maintain gentle negative pressure on the syringe plunger as you advance to identify intravascular placement and prevent an intravascular injection.
If blood returns into the syringe, stop advancing, hold the syringe in place, and now regard this needle as a finder needle. Assess the blood return and use this needle to guide introduction of the introducer needle.
Insert the introducer needle (or finder needle, optional)
Insert the introducer needle (with needle bevel directed anteriorly, aligned along the insertion path).
Maintain gentle negative pressure on the syringe plunger as you advance the needle.
Stop advancing when a flash of blood appears in the barrel of the syringe (you may feel the needle pop through the wall as it enters the lumen). Hold the syringe motionless in this spot. Even a slight movement may displace the needle tip from the vein.
If cannulation is difficult, a small towel rolled under the patient's ipsilateral shoulder or caudal traction (5 cm) on the arm may be tried.
If no flash of blood appears in the barrel after 3 to 4 cm of insertion, withdraw the needle slowly. If the needle had initially passed completely through the vein, a flash may now appear as you withdraw the needle tip back into the lumen. If a flash still does not appear, withdraw the needle almost to the skin surface, change direction, and try again to advance the needle into the vein. Do not change direction of the needle while it is fully inserted.
Once venous blood return is confirmed, rotate the needle so the bevel faces inferiorly (toward the feet and the heart, away from the internal jugular vein). Advance the J-tipped guidewire with the curve pointing in that same direction.
Typical adult insertion depth is about 15 cm on the right and 16 to 17 cm on the left for a landmark infraclavicular puncture.
Assess the blood return
Continue to hold the syringe motionless.
Securely grasp the needle hub and also hold it motionless.
Remove the syringe from the needle hub and briefly let blood flow out to confirm that the blood is venous (ie, dark red and flowing but not pulsatile). Then immediately cover the hub with your thumb to stop the blood flow and prevent air embolism.
However, if the blood is bright red and pulsatile (arterial), terminate the procedure. Remove the needle and use gauze squares for 10 minutes to hold external pressure on the area to decrease bleeding from the puncture site. Patients should be closely monitored for the development of hemothorax and hemorrhage (eg, serial vital signs, physical examination, possibly a chest radiograph). If the artery is punctured with the dilator, leave it in place and consult vascular surgery immediately.
If it is unclear whether the blood is arterial, attach a short piece of clear IV tubing to the needle; if the blood rises rapidly or pulsates up the tube, it is arterial. The operator can also attach the pressure transducer to the needle directly to check for a venous waveform prior to dilating. Note that arterial blood can appear dark with sluggish flow in hypoxia, shock, hypotension, or cardiac arrest.


Optional: Use the finder needle to guide insertion of the introducer needle
If up to this point you have been inserting a finder needle (or an anesthetic needle that found the vein), now you will use this needle to guide insertion of the introducer needle.
Hold the introducer syringe with the needle bevel facing down.
Use one of two insertion methods: Either remove the finder needle and immediately insert the introducer needle along the same path, or keep the finder needle in place and insert the introducer needle inferiorly alongside it but directed slightly superiorly to aim toward the same venipuncture point as the finder needle.
Stop advancing the introducer needle and hold it motionless when a flash of blood appears in the barrel of the syringe.
If the finder needle has not been removed, remove it now.
Subclavian Venipuncture
This figure shows hand position during subclavian venipuncture (infraclavicular approach). |

Insert the guidewire
Carefully rotate the introducer syringe such that the bevel of the needle now faces inferiorly (ie, away from the internal jugular vein and toward the heart).
Insert the J-curved end of the guidewire into the introducer needle, with the J curve facing inferiorly (ie, in the same direction as the needle bevel).
Advance the guidewire through the needle and into the vein. Do not force the guidewire; it should slide smoothly. Advance the guidewire 20 to 23 cm or until ectopic heartbeats occur (withdraw the guidewire from this point until ectopy stops).
If you feel any resistance as you advance the guidewire, stop advancing it. Try to gently withdraw the guidewire slightly, rotate it slightly, and then re-advance it, or try to gently withdraw the guidewire entirely, reestablish the needle tip within the vein (confirmed by venous blood return), and then reinsert the guidewire.
However, if you feel any resistance as you withdraw the guidewire, terminate the procedure and withdraw the needle and guidewire together as a unit (to prevent the needle tip from shearing through the guidewire within the patient). Then use gauze squares for 10 minutes to hold external pressure on the area and to help prevent bleeding and hematoma.
Once the guidewire has been inserted, continue to hold it securely in place with one hand and maintain control of it throughout the remainder of the procedure to avoid wire embolism.
Remove the introducer needle (after successful guidewire insertion)
First, securely hold the guidewire distal to the needle and pull the needle from the skin.
Then, securely hold the guidewire at the skin surface and slide the needle down the remaining length of the guidewire to remove the needle.
Widen the insertion tract
Extend the skin insertion site: Using the scalpel, make a small stab incision (approximately 4 mm) into the skin insertion site, avoiding contact with the guidewire, to enlarge the site and allow it to accommodate the larger diameters of the tissue dilator and the catheter.
Advance the tissue dilator over the guidewire: First, grasp the guidewire at the skin and slide the dilator down the length of the guidewire to the skin. Then grasp the guidewire just distal to the dilator, hold the dilator near the skin surface, and use a corkscrew motion as needed to slowly advance the dilator through the skin and soft tissue until the dilator just passes through the wall of the vein. There is sometimes a loss of resistance from advancing the dilator as it passes under the clavicle. Maintain your grasp on the guidewire at all times during the insertion.
Remove the dilator: First, securely hold the guidewire distal to the dilator and pull the dilator from the skin. When the guidewire is visible at the skin surface, completely remove the dilator by sliding it down the remaining length of the guidewire.
Maintain your grasp on the guidewire at the skin surface.
If the artery is punctured with the dilator, leave it in place and consult vascular surgery immediately.
Place the catheter
Advance the catheter over the guidewire to the skin surface: Hold the guidewire fixed at the skin surface, thread the catheter tip over the distal end of the guidewire, and slide the catheter down to the skin surface. The distal end of the guidewire should now be protruding from the port hub.
If the distal end of the guidewire is not protruding from the port hub, incrementally advance the guidewire outward from the skin surface while holding the catheter tip close to the surface until the guidewire protrudes.
Continue to advance the catheter into the vein: Grasp and control the guidewire where it protrudes from the hub. Hold the catheter near its tip and insert the tip through the skin. Then, in increments of several centimeters and using a corkscrew motion as necessary, stepwise advance the entire length of the subclavian catheter. If ectopic heartbeats occur, slowly withdraw the catheter until ectopy stops.
Maintain your grasp on both the guidewire and the catheter.
Remove the guidewire: Withdraw the guidewire while holding the catheter securely in place at the skin surface.
Flush each catheter port with saline: First, draw any air from the line and confirm venous blood flow into the hub. Then, using a 10-mL syringe (or one of equal or greater diameter) and without using excessive force, push 20 mL of saline into the line to clear it.
Dress the site
If the patient is awake or minimally sedated, use 1% lidocaine to anesthetize the skin at the planned suture locations.
Place a chlorhexidine-impregnated disk on the skin at the catheter insertion point.
Suture the skin to the mounting clip on the catheter.
To prevent pulling on the insertion site, suture the catheter at a second site so that a curved or looped segment of catheter lies between the 2 sites.
Apply a sterile occlusive dressing. Transparent membrane dressings are commonly used.
Aftercare for Infraclavicular Subclavian Vein Cannulation
Perform chest radiography to confirm that the tip of a subclavian (or jugular) CVC lies in the superior vena cava near its junction with the right atrium (the catheter can be advanced or retracted if not in the appropriate position) and to confirm that pneumothorax has not occurred.

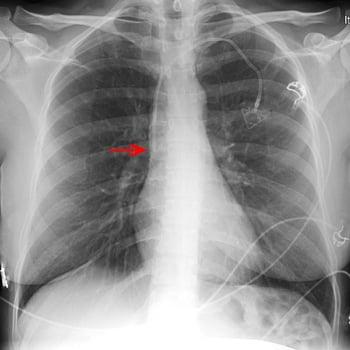
The red arrow points to the tip of a left subclavian venous port catheter (placed appropriately in the lower superior vena cava).
Warnings and Common Errors for Infraclavicular Subclavian Vein Cannulation
Placing a pillow under the patient's back to facilitate subclavian line placement may hinder correct placement by narrowing the space between the clavicle and first rib.
The tip of a CVC must never lie in the right atrium because the atrium is thin-walled and easily perforated.
Cardiac ectopy may be induced by a guidewire or catheter in the right atrium or ventricle.
Never lose grasp of the guidewire.
During cardiopulmonary arrest, or even low blood pressure and hypoxia, arterial blood may be dark and not pulsatile and may be mistaken for venous blood.
To help prevent air embolism, CVCs should be inserted (and removed) with the vascular cannulation site positioned dependant to the heart.
References
1. O'Grady NP. Prevention of Central Line-Associated Bloodstream Infections. N Engl J Med. 2023;389(12):1121-1131. doi:10.1056/NEJMra2213296
2. Zawadka M, La Via L, Wong A, et al. Real-Time Ultrasound Guidance as Compared With Landmark Technique for Subclavian Central Venous Cannulation: A Systematic Review and Meta-Analysis With Trial Sequential Analysis. Crit Care Med. 2023;51(5):642-652. doi:10.1097/CCM.0000000000005819
3. Practice Guidelines for Central Venous Access 2020: An Updated Report by the American Society of Anesthesiologists Task Force on Central Venous Access. Anesthesiology. 2020;132(1):8-43. doi:10.1097/ALN.0000000000002864
4. Frankel HL, Kirkpatrick AW, Elbarbary M, et al. Guidelines for the Appropriate Use of Bedside General and Cardiac Ultrasonography in the Evaluation of Critically Ill Patients-Part I: General Ultrasonography. Crit Care Med. 2015;43(11):2479-2502. doi:10.1097/CCM.0000000000001216
5. Franco-Sadud R, Schnobrich D, Mathews BK, et al. Recommendations on the Use of Ultrasound Guidance for Central and Peripheral Vascular Access in Adults: A Position Statement of the Society of Hospital Medicine. J Hosp Med. 2019;14(9):E1-E22. doi:10.12788/jhm.3287
6. Teja B, Bosch NA, Diep C, et al. Complication Rates of Central Venous Catheters: A Systematic Review and Meta-Analysis. JAMA Intern Med. 2024;184(5):474-482. doi:10.1001/jamainternmed.2023.8232
7. Patel IJ, Rahim S, Davidson JC, et al. Society of Interventional Radiology Consensus Guidelines for the Periprocedural Management of Thrombotic and Bleeding Risk in Patients Undergoing Percutaneous Image-Guided Interventions-Part II: Recommendations: Endorsed by the Canadian Association for Interventional Radiology and the Cardiovascular and Interventional Radiological Society of Europe. J Vasc Interv Radiol. 2019;30(8):1168-1184.e1. doi:10.1016/j.jvir.2019.04.017
8. Carroll MI, Ahanchi SS, Kim JH, Panneton JM. Endovascular foreign body retrieval. J Vasc Surg. 2013;57(2):459-463. doi:10.1016/j.jvs.2012.01.092
9. Buetti N, Marschall J, Drees M, et al. Strategies to prevent central line-associated bloodstream infections in acute-care hospitals: 2022 Update. Infect Control Hosp Epidemiol. 2022;43(5):553-569. doi:10.1017/ice.2022.87
10. Calvache JA, Rodríguez MV, Trochez A, Klimek M, Stolker RJ, Lesaffre E. Incidence of Mechanical Complications of Central Venous Catheterization Using Landmark Technique: Do Not Try More Than 3 Times. J Intensive Care Med. 2016;31(6):397-402. doi:10.1177/0885066614541407
11. Schummer W, Schummer C, Rose N, Niesen WD, Sakka SG. Mechanical complications and malpositions of central venous cannulations by experienced operators. A prospective study of 1794 catheterizations in critically ill patients. Intensive Care Med. 2007;33(6):1055-1059. doi:10.1007/s00134-007-0560-z
Drug Information for the Topic







