


Acute viral hepatitis is diffuse liver inflammation caused by specific hepatotropic viruses that have diverse modes of transmission and epidemiologies. Although acute viral hepatitis can be asymptomatic, a nonspecific viral prodrome is often followed by anorexia, nausea, and often fever or right upper quadrant pain. Jaundice can develop, typically as other symptoms begin to resolve. Most cases resolve spontaneously, but some progress to chronic hepatitis. Occasionally, acute viral hepatitis progresses to acute liver failure (indicating acute liver failure). Diagnosis is by liver tests and serologic tests to identify the virus. Universal precautions, food safety, and hygiene can prevent transmission of acute viral hepatitis. Depending on the specific virus, preexposure and postexposure prophylaxis may be possible using vaccines or serum globulins. Treatment is supportive or with antiviral therapy, depending on the specific virus.
(See also Causes of Hepatitis and Neonatal Hepatitis B Virus Infection.)
Acute viral hepatitis is a common, worldwide disease that has different causes; each type shares clinical, biochemical, and morphologic features. The term acute viral hepatitis often refers to infection of the liver by one of the hepatitis viruses. Other viruses (eg, Epstein-Barr virus, yellow fever virus, cytomegalovirus, and adeno-associated virus) (1) can also cause acute viral hepatitis, but less commonly.

General reference
1. Rodriguez-Frias F, Rando-Segura A, Quer J. Solved the enigma of pediatric severe acute hepatitis of unknown origin?. Front Cell Infect Microbiol. 2023;13:1175996. Published 2023 Sep 21. doi:10.3389/fcimb.2023.1175996
Etiology of Acute Viral Hepatitis
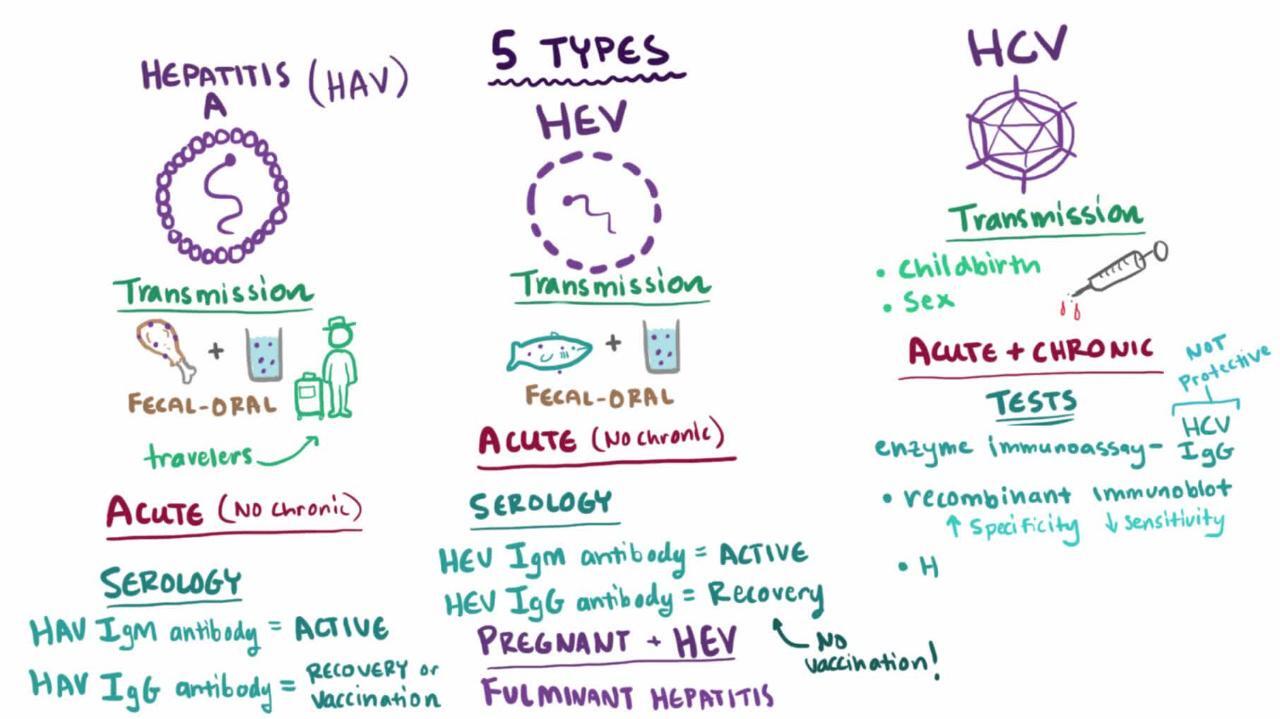
At least 5 specific viruses appear to be responsible for acute viral hepatitis (see table ):
Hepatitis A (HAV)
Hepatitis B (HBV)
Hepatitis C (HCV)
Hepatitis D (HDV)
Hepatitis E (HEV)
Other unidentified viruses probably also cause acute viral hepatitis (1).
Characteristics of Hepatitis Viruses
Characteristic | Hepatitis A Virus | Hepatitis B Virus | Hepatitis C Virus | Hepatitis D Virus | Hepatitis E Virus |
|---|---|---|---|---|---|
Nucleic acid | RNA | DNA | RNA | * | RNA |
Serologic diagnosis | IgM anti-HAV (acute infection); total anti‑HAV (immunity) | HBsAg (active infection); IgM anti‑HBc (acute infection) | Anti-HCV (screening); HCV RNA (confirmation of active infection) | Anti-HDV; HDV RNA (active infection; requires HBsAg positivity) | IgM Anti-HEV (acute infection); HEV RNA (if available) |
Major transmission | Fecal-oral | Blood | Blood | Needle | Water |
Incubation period (days) | 15–50 | 40–180† | 15–85‡ | 20–50§ | 15–40¶ |
Epidemics | Yes | No | No | No | Yes |
Chronicity | No | Yes | Yes | Yes | Rare |
Liver cancer | No | Yes | Yes | Yes | No |
* Incomplete RNA; requires presence of hepatitis B virus for replication. † Workowski KA, Bachmann LH, Chan PA, et al. Sexually Transmitted Infections Treatment Guidelines, 2021. MMWR Recomm Rep. 2021;70(4):1-187. Published 2021 Jul 23. doi:10.15585/mmwr.rr7004a1 ‡ Maheshwari A, Ray S, Thuluvath PJ. Acute hepatitis C. Lancet. 2008;372(9635):321-332. doi:10.1016/S0140-6736(08)61116-2 § Farci P, Niro GA. Clinical features of hepatitis D. Semin Liver Dis. 2012;32(3):228-236. doi:10.1055/s-0032-1323628 ¶ Kamar N, Bendall R, Legrand-Abravanel F, et al. Hepatitis E. Lancet. 2012;379(9835):2477-2488. doi:10.1016/S0140-6736(11)61849-7 | |||||
IgM anti-HAV = IgM antibody to hepatitis A virus; HBsAg = hepatitis B surface antigen; HBc = hepatitis B core antigen; Anti-HCV = antibody to hepatitis C virus; anti-HDV = antibody to hepatitis D virus; anti-HEV = antibody to hepatitis E virus. | |||||
Etiology reference
1. Tassopoulos NC, Papatheodoridis GV, Delladetsima I, et al. Clinicopathological features and natural history of acute sporadic non-(A-E) hepatitis. J Gastroenterol Hepatol. 2008;23(8 Pt 1):1208-1215. doi:10.1111/j.1440-1746.2008.05454.x
Symptoms and Signs of Acute Viral Hepatitis
Some manifestations of acute hepatitis are virus-specific (see discussions of individual hepatitis viruses) and some patients are asymptomatic, but in general, acute infection tends to develop in predictable phases:
Incubation period: The virus multiplies and spreads without causing symptoms (see table ).
Prodromal (pre-icteric) phase: Nonspecific symptoms occur; they include profound anorexia, malaise, nausea and vomiting, a newly developed distaste for cigarettes (in people who smoke), and often fever or right upper quadrant abdominal pain. Urticaria and arthralgias occasionally occur, especially in HBV infection.
Icteric phase: After 3 to 10 days, the urine darkens, followed by jaundice. Systemic symptoms often regress, and patients feel better despite worsening jaundice. The liver is usually enlarged and tender, but the edge of the liver remains soft and smooth. Mild splenomegaly occurs in some patients. Jaundice usually peaks within 1 to 2 weeks.
Recovery phase: During this 2- to 4-week period, jaundice fades.
Appetite usually returns after the first week of symptoms. Acute viral hepatitis usually resolves spontaneously 4 to 8 weeks after symptom onset.
Anicteric hepatitis (hepatitis without jaundice) occurs more often than icteric hepatitis in patients with hepatitis C virus (HCV) infection and in children with hepatitis A virus (HAV) infection (1, 2, 3). It typically manifests as a minor flu-like illness.
Recrudescent hepatitis occurs in a few patients and is characterized by recurrent manifestations during the recovery phase.
Manifestations of cholestasis may develop during the icteric phase (called cholestatic hepatitis) but usually resolve. When they persist, they cause prolonged jaundice, elevated alkaline phosphatase, and pruritus, despite general regression of inflammation.
Symptoms and signs references
1. Martinello M, Solomon SS, Terrault NA, et al. Hepatitis C. Lancet. 2023;402(10407):1085-1096. doi:10.1016/S0140-6736(23)01320-X
2. Nelson NP, Weng MK, Hofmeister MG, et al. Prevention of Hepatitis A Virus Infection in the United States: Recommendations of the Advisory Committee on Immunization Practices, 2020. MMWR Recomm Rep. 2020;69(5):1-38. Published 2020 Jul 3. doi:10.15585/mmwr.rr6905a1
3. Hofmeister M, Weng M. Hepatitis A. CDC Yellow Book: Health Information for International Travel. April 23, 2025. Accessed May 12, 2026.
Diagnosis of Acute Viral Hepatitis
Liver tests (aspartate aminotransferase [AST] and alanine aminotransferase [ALT] elevated out of proportion to alkaline phosphatase, usually with hyperbilirubinemia)
Viral serologic and nucleic acid amplification (NAAT) testing
Prothrombin/international normalized ratio (PT/INR) measurement
Initial diagnosis of acute hepatitis
Acute hepatitis must first be differentiated from other disorders that cause similar symptoms. In the prodromal phase, hepatitis mimics various nonspecific viral illnesses and is difficult to diagnose. Anicteric patients suspected of having hepatitis based on risk factors are tested initially with liver tests, including aminotransferases, bilirubin, and alkaline phosphatase. Acute hepatitis often manifests in the icteric phase and so should be differentiated from other disorders causing jaundice (see figure Simplified Diagnostic Approach to Possible Acute Viral Hepatitis).


This photo shows yellowing of the sclera of the eyes and the skin on the face.
DR P. MARAZZI/SCIENCE PHOTO LIBRARY


This photo shows icterus, or jaundice, of the conjunctivae and facial skin, caused by the hepatitis A virus.
CDC
Acute hepatitis can usually be differentiated from other causes of jaundice by:
Often severe elevations of AST and ALT≥ 15 times the upper limit of normal (1)
ALT is typically higher than AST, but absolute levels correlate poorly with clinical severity. Values increase early in the prodromal phase, peak before jaundice is maximal, and fall slowly during the recovery phase. Urinary bilirubin usually precedes jaundice. Hyperbilirubinemia in acute hepatitis varies in severity, and fractionation has no clinical value. Alkaline phosphatase is usually only moderately elevated; marked elevation suggests extrahepatic cholestasis and prompts imaging tests (eg, ultrasound).
Liver biopsy is usually not needed unless the diagnosis is uncertain.
If laboratory results suggest acute hepatitis, particularly if ALT and AST are > 1000 IU/L (16.7 microkat/L), PT/INR is measured to assess liver synthetic function of clotting factors.
Manifestations of portosystemic encephalopathy combined with bleeding diathesis or prolongation of INR suggest acute liver failure, indicating acute liver failure.
If acute hepatitis is suspected, efforts are next directed toward identifying its cause. A history of exposure may provide the only clue of drug-induced or toxic hepatitis. The history should also elicit risk factors for viral hepatitis.
Prodromal sore throat and diffuse adenopathy suggest infectious mononucleosis rather than viral hepatitis.
Simplified Diagnostic Approach to Possible Acute Viral Hepatitis
* Obtain additional laboratory studies for hepatitis A (see table Hepatitis A Serology), hepatitis B (see table Hepatitis B Serology), and hepatitis C (see table Hepatitis C Serology). ALT = alanine aminotransferase; anti-HCV = antibody to hepatitis C virus; AST = aspartate aminotransferase; HBcAg = hepatitis B core antigen; HBsAg = hepatitis B surface antigen; IgM = immunoglobulin M; IgM anti-HAV = IgM antibody to hepatitis A virus; PCR = polymerase chain reaction; RNA = ribonucleic acid. |


Serology and nucleic acid amplification testing
In patients with findings suggesting acute viral hepatitis, the following studies are performed to test for hepatitis viruses A, B, and C:
Hepatitis A virus: IgM antibody to HAV (IgM anti-HAV) (acute infection); total anti‑HAV (immunity)
Hepatitis B virus: Hepatitis B surface antigen (HBsAg) and IgM antibody to hepatitis B core antigen (IgM anti-HBc)
Hepatitis C virus: Antibody to HCV (anti-HCV) with reflex quantitative hepatitis C RNA polymerase chain reaction (HCV-RNA PCR)
Hepatitis E virus (selected patients): IgM anti-HEV and HEV-RNA PCR
If any are positive, further serologic testing may be necessary to differentiate acute from past or chronic infection (see tables , , and ).
If serologically confirmed HBV infection is severe, anti-HDV is measured.
If the patient has recently traveled to an endemic area or is immunosuppressed, IgM antibody to HEV (IgM anti-HEV) and HEV-RNA should be measured. Some experts recommend that HEV testing be included in the initial investigation of any patient with acute hepatitis (2).
Biopsy
Biopsy is usually unnecessary but, if performed, usually reveals similar histopathology regardless of the specific virus:
Patchy cell dropout
Acidophilic hepatocellular necrosis
Mononuclear inflammatory infiltrate
Histologic evidence of regeneration
Preservation of the reticulin framework
HBV infection can occasionally be diagnosed based on the presence of ground-glass hepatocytes (caused by HBsAg-packed cytoplasm) and using special immunologic stains for the viral components. However, these findings are unusual in acute HBV infection and are much more common in chronic HBV infection.
Diagnosis references
1. Kwo PY, Cohen SM, Lim JK. ACG Clinical Guideline: Evaluation of Abnormal Liver Chemistries. Am J Gastroenterol. 2017;112(1):18-35. doi:10.1038/ajg.2016.517
2. European Association for the Study of the Liver. EASL Clinical Practice Guidelines on hepatitis E virus infection. J Hepatol. 2018;68(6):1256-1271. doi:10.1016/j.jhep.2018.03.005
Treatment of Acute Viral Hepatitis
Supportive care
Treatment of acute hepatitis C, partly to prevent transmission to others
Alcohol and hepatotoxic medications should be avoided because they can increase liver damage. Restrictions on diet or activity, including commonly prescribed bed rest, have no scientific basis.
Patients with acute HCV infection should be treated with antiviral therapy upon initial diagnosis. Owing to the high efficacy and safety, the same regimens that are recommended for chronic HCV infection are recommended for acute infection (1).
Most adults with acute hepatitis B recover spontaneously and require only supportive care. Antiviral therapy is recommended only for severe cases, including acute liver failure or significant hepatic dysfunction, with tenofovir or entecavir as the preferred agents.
For cholestatic hepatitis, cholestyramine 8 g orally once or twice a day can relieve itching.
Viral hepatitis should be reported to the local or state health department.
Treatment reference
1. American Association for the Study of Liver Diseases (AASLD) and Infection Diseases Society of America (IDSA). Management of Acute HCV Infection. Published February 22, 2017. Accessed April 24, 2026.
Prevention of Acute Viral Hepatitis
Because treatments have limited efficacy, prevention of viral hepatitis is very important.
General measures
Good personal hygiene and safe water and food handling helps prevent transmission, particularly fecal-oral transmission as occurs with hepatitis A virus (HAV) infection and hepatitis E virus (HEV) infection. Isolation of patients does little to prevent spread of HAV.
Blood and other body fluids (eg, saliva, semen) of patients with acute HBV and HCV infection and stool of patients with HAV infection are considered infectious. Barrier protection is recommended for all sexual contact to prevent the spread of hepatitis B virus (HBV), and for men who have sex with men to prevent the spread of hepatitis C virus (HCV) (1, 2). Isolation of patients is of no value in preventing HBV or HCV infection.
Posttransfusion infection is minimized by avoiding unnecessary transfusions and by screening all donors for hepatitis B and C. Screening has decreased the incidence of posttransfusion hepatitis B and hepatitis C, which are now extremely rare in the United States (3).
Immunoprophylaxis
Immunoprophylaxis can involve active immunization using vaccines and passive immunization.
Vaccines for HAV and HBV are available in the United States.
Routine vaccination for HAV and HBV is recommended by some expert organizations for all children, and for adults at high risk.
A vaccine for hepatitis E virus (HEV) is not available in the United States but is available in China and Pakistan (4).
Standard immune globulin prevents or decreases the severity of HAV infection and should be given to nonimmune family members and close contacts of patients (postexposure prophylaxis), as well as for pre-exposure prophylaxis in those who cannot or do not receive the vaccine (5).
Hepatitis B immune globulin (HBIG) is used along with the hepatitis B vaccine for postexposure prophylaxis and in neonates born to mothers with known or possible hepatitis B (see Neonatal Hepatis B Infection) (6).
No product exists for immunoprophylaxis of HCV or hepatitis D virus (HDV). However, prevention of HBV infection prevents HDV infection. The propensity of HCV for changing its genome hampers vaccine development.
References
1. AASLD and IDSA. HCV in Key Populations: Men Who Have Sex With Men. Published April 13, 2028. Accessed May 12, 2026.
2. Workowski KA, Bachmann LH, Chan PA, et al. Sexually Transmitted Infections Treatment Guidelines, 2021. MMWR Recomm Rep. 2021;70(4):1-187. Published 2021 Jul 23. doi:10.15585/mmwr.rr7004a1
3. Dodd RY, Crowder LA, Haynes JM, et al. Screening Blood Donors for HIV, HCV, and HBV at the American Red Cross: 10-Year Trends in Prevalence, Incidence, and Residual Risk, 2007 to 2016. Transfus Med Rev. 2020;34(2):81-93. doi:10.1016/j.tmrv.2020.02.001
4. Huang S, Zhang X, Su Y, et al. Long-term efficacy of a recombinant hepatitis E vaccine in adults: 10-year results from a randomised, double-blind, placebo-controlled, phase 3 trial. Lancet. 2024;403(10429):813-823. doi:10.1016/S0140-6736(23)02234-1
5. Nelson NP, Weng MK, Hofmeister MG, et al. Prevention of Hepatitis A Virus Infection in the United States: Recommendations of the Advisory Committee on Immunization Practices, 2020. MMWR Recomm Rep. 2020;69(5):1-38. Published 2020 Jul 3. doi:10.15585/mmwr.rr6905a1
6. Poland GA, Jacobson RM. Clinical practice: prevention of hepatitis B with the hepatitis B vaccine. N Engl J Med. 2004;351(27):2832-2838. doi:10.1056/NEJMcp041507
Key Points
Transmission is the fecal-oral route for hepatitis A and E parenterally or via blood for hepatitis B and C.
Hepatitis B and C, unlike hepatitis A, predispose to chronic hepatitis and therefore liver cancer.
Patients with acute viral hepatitis (especially hepatitis C) may be anicteric or even asymptomatic.
Perform viral serologic and nucleic acid amplification testing (NAAT) (for HAV, HBV, HCV, and sometimes HEV) if clinical findings are consistent with acute viral hepatitis and AST and ALT are elevated out of proportion to alkaline phosphatase.
Treat acute hepatitis C with direct-acting antiviral medications.
Routine vaccination for hepatitis A and B is recommended in the United States.
Drug Information for the Topic







