


Painful sex in women, called genito-pelvic pain/penetration disorder, includes pain during sexual intercourse or other sexual activity that involves penetration and involuntary contraction of muscles around the opening of the vagina (levator ani syndrome, or vaginismus), making sexual intercourse painful or impossible.
Most women with pain during sex are anxious about and cannot tolerate insertion of any object into the vagina (such as a penis, a tampon, or a speculum [during a pelvic examination]).
Women may develop genito-pelvic pain/penetration disorder after experiencing painful intercourse (due to vaginal dryness or sexual trauma), or there may be no known cause.
Doctors diagnose genito-pelvic pain/penetration disorder based on symptoms, a pelvic examination, and specific criteria.
Lubricants, topical anesthetic (numbing) gels, exercises to relax pelvic muscles, exercises to make women feel comfortable with vaginal contact by themselves or their partner, or pelvic physical therapy may help.
Pain during intercourse may occur in the
Vulva (the external female genitals, including the labia, clitoris, and opening of the vagina), called provoked vestibulodynia: Occurring when the vulva is touched, even with light pressure
Vagina, called dyspareunia: Occurring when something is inserted into the vagina
Abdomen (belly), called deep dyspareunia: Occurring in the abdomen when something is inserted into the vagina
The pain may be burning, sharp, or cramping. Pelvic muscles tend to become tight, which increases the pain, whether it is superficial or deep.
In genito-pelvic pain/penetration disorder, muscles around the opening of vagina tighten involuntarily when a woman thinks about or tries to have sexual intercourse (or any vaginal insertion, such as during a pelvic examination).
Many women with genito-pelvic pain/penetration disorder also have difficulty becoming aroused and/or difficulty reaching orgasm.
External Female Reproductive Anatomy

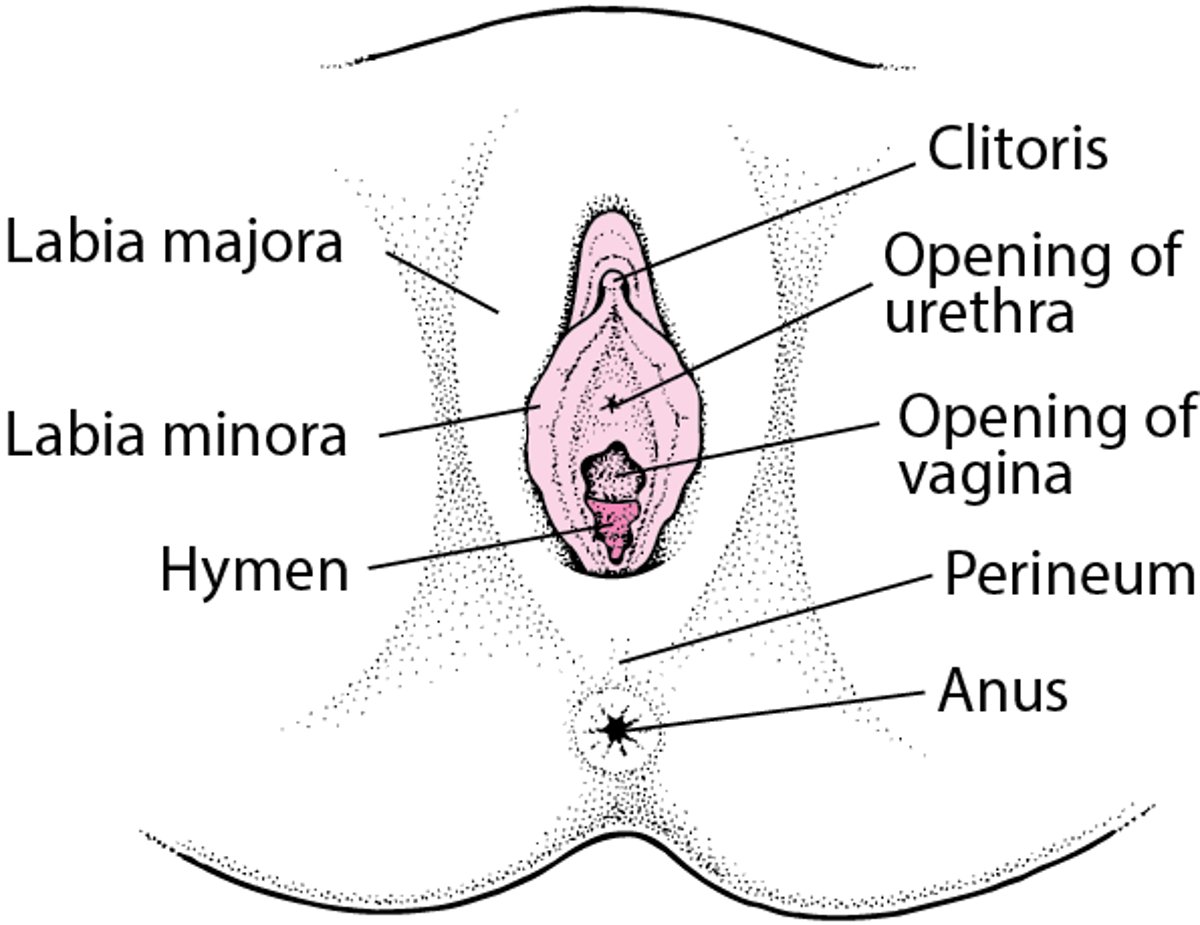
Causes of Genito-Pelvic Pain/Penetration Disorder
Genito-pelvic pain/penetration disorder can be caused by 1 or more factors. It is influenced by a combination of physical, psychological, relationship, and social or cultural factors.
Physical (biological) causes may include medical conditions that affect the pelvic area, such as pelvic floor muscle problems, endometriosis, or vaginal infections (like yeast infections or bacterial vaginosis). Hormonal changes, such as those related to menopause or birth control use, can also lead to vaginal dryness or thinning of the vaginal tissues, which can cause pain during sexual activity.
Psychological factors can also play an important role. Women with genito-pelvic pain/penetration disorder are more likely to have a history of sexual, emotional, or physical trauma. Painful sexual experiences in the past may lead to anxiety about future sexual activity, causing the pelvic muscles to tighten, which can increase pain and lead to avoidance of sexual activity over time. Certain thought patterns, such as worrying excessively about pain, having unrealistic expectations about sex, or focusing too much on physical symptoms, can make pain more likely or more severe.
Relationship factors can also affect symptoms. A partner’s response to pain can influence how symptoms develop or continue. For example, negative or overly concerned reactions from a partner may worsen distress or pain, while supportive and understanding responses may help improve outcomes.
Social and cultural factors may also contribute. These can include limited or inaccurate sexual education, misunderstandings about sex, cultural or religious beliefs that create negative feelings about sexuality, and stress. All of these can play a role in how pain develops and continues over time.
Specific causes of genito-pelvic pain/penetration disorder vary depending on whether the pain is superficial or deep.
Vulvar pain
Vulvar pain may result from the following:
Genitourinary syndrome of menopause (changes in the vagina and urinary tract that can occur at menopause)
Inadequate lubrication from insufficient foreplay
Inflammation or infection in the genital area (including genital herpes and yeast infections or Bartholin gland infections)
An allergic reaction to contraceptive foams or jellies or to latex condoms
Injuries in the genital area
Pain every time the vulva or vaginal opening is touched or comes into contact with clothing or other surfaces, even if the contact is gentle (called provoked vulvodynia or vestibulodynia) or constant vulvar pain without an identifiable cause (unprovoked vulvodynia or vestibulodynia)
Breastfeeding, which can cause dryness of the vagina because estrogen levels are low
Inflammation or infection of the urinary tract
Genitourinary syndrome of menopause refers to changes in the vagina and urinary tract that occur after menopause caused by a decrease in estrogen levels. Tissues of the vagina can become thin, dry, and have difficulty stretching, and lubrication for intercourse is inadequate.
The causes of vulvodynia (pain of the labia) or vestibulodynia (pain of the opening of the vagina, called the vaginal vestibule) are uncertain. These symptoms may begin for no known reason or they may develop after a possible triggering event, such as a vaginal infection or after menopause.
Vaginal pain
Vaginal pain during or after sexual intercourse may result from the following:
Vaginitis (bacterial vaginosis, yeast infections, or trichomonal infection)
Genitourinary syndrome of menopause (changes in the vagina and urinary tract that can occur at menopause)
Vaginismus (increased pelvic floor muscle tension)
Myofascial pain (pain that is caused by tension and tenderness in areas of muscle called trigger points)
The term vaginismus (also called levator ani syndrome) is involuntary contraction of the levator ani, which is the main pelvic floor muscle. Often, the cause of this disorder in unknown, but it can develop after sexual trauma or the experience of painful intercourse under any circumstances or a painful pelvic examination. If women fear sex will be painful, their pelvic muscles may automatically tighten whenever intercourse is anticipated or attempted.
Rarely, an abnormality of the vagina is present at birth, with tissue blocking the opening. The can result in pain with attempted vaginal intercourse.
Deep abdominal pain
Pain deep in the abdomen during or after sexual intercourse may result from the following:
Infection of the cervix, uterus, or fallopian tubes (pelvic inflammatory disease)
Myofascial pain
Growths in the pelvis (such as tumors and ovarian cysts)
Bands of scar tissue (adhesions) between organs in the pelvis, which may form after an infection, surgery, or radiation therapy for cancer in a pelvic organ (such as the bladder, uterus, cervix, fallopian tubes, or ovaries)
Symptoms of Genito-Pelvic Pain/Penetration Disorder
The pain of genito-pelvic pain/penetration disorder may first occur when something (tampon, speculum, or penis) is inserted into the vagina. Or a woman may never have had pain-free sexual intercourse. For example, the pain may occur even if she has not had sexual pain in the past. The pain is often described as burning or stabbing.
Women with genito-pelvic pain/penetration disorder may have an intense fear of and anxiety about pain before or during penetration of the vagina. When women anticipate that pain will recur during penetration, their vaginal muscles tighten, making attempts at sexual intercourse even more painful.
The inability to have sexual intercourse is stressful for a woman and can cause relationship stress with a partner. It causes significant stress for a woman who wants to become pregnant.
Diagnosis of Genito-Pelvic Pain/Penetration Disorder
Doctor's evaluation, based on standard psychiatric criteria
Doctors diagnose genito-pelvic pain/penetration disorder based on a woman’s medical history and description of the problem, including when and where the pain is felt, and on the results of a pelvic examination. A pelvic examination can detect or rule out physical abnormalities.
If a woman has a history of vaginal pain, the anticipation of pain and involuntary contraction of muscles around the vagina's opening can make it difficult to have a pelvic examination. This can be discussed with the doctor before the examination. Some strategies for making a pelvic examination more tolerable are as follows:
A woman and her doctor can discuss the examination before it begins and agree on how to communicate during the examination.
A woman can hold a mirror to be able to see what the doctor sees during the examination and allow the doctor to show her any issues that are detected.
A woman can place her hand on the doctor’s hand to have a greater sense of control during the examination.
The area in and around the opening of the vagina is examined for possible causes, such as signs of inflammation or other abnormalities.
To determine where the pain occurs, a doctor may use a cotton swab to touch different areas around and/or in the vagina.
Doctors may also press on the urethra and bladder to check for tenderness.
The doctor assesses the tightness of the pelvic muscles around the vagina by inserting 1 or 2 gloved fingers into the vagina. To check the uterus and ovaries for abnormalities, the doctor then places the other hand on the lower abdomen (called a bimanual examination) and presses on these organs.
Doctors diagnose genito-pelvic pain/penetration disorder based on standard psychiatric criteria. These criteria require the presence of at least 1 of the following:
Significant pain during intercourse or penetration attempts
Significant fear of or anxiety about pain in anticipation of, during, or because of vaginal penetration
Significant tensing or tightening of the pelvic muscles during attempts to penetrate the vagina
These symptoms must have been present for at least 6 months and must cause significant distress in a woman. Also, doctors must rule out any other cause of the symptoms, such as another disorder, sexual trauma, or medication or other substance.
Treatment of Genito-Pelvic Pain/Penetration Disorder
Treatment of the cause of the pain, if possible
Education about chronic pain and its effects on sexuality
Lubricants, sometimes anesthetic (numbing) gels
Pelvic floor physical therapy
Psychological therapies
Management of genito-pelvic pain/penetration disorder (GPPPD) should take a whole-person (biopsychosocial) approach, taking into consideration physical, psychological, relationship, and social or cultural factors. Treatment often involves working with different specialists, such as a gynecologist or pelvic floor physical therapist for physical symptoms, and a psychologist or sex therapist for emotional and relationship concerns.
The first step is to treat any physical causes, if they can be identified. These may include conditions such as vaginal dryness related to menopause, painful intercourse, vaginismus, or vulvodynia.
General measures
If dryness is an issue, vaginal lubricants and moisturizers, including food-based oils (such as coconut oil), silicone-based lubricants, and water-based products, are used. Water-based lubricants dry out quickly and may have to be reapplied, but they are preferred over petroleum jelly or other oil-based lubricants. Oil-based lubricants tend to dry the vagina and can damage latex prophylactic devices such as condoms and diaphragms. They should not be used with condoms. Silicone-based lubricants can be used with condoms and diaphragms, as can water-based lubricants. Women can ask their doctor which type of lubricant would be best for them.
General measures for vaginal health include wearing cotton underwear, possibly wearing no underwear while sleeping, washing only with water or a mild soap, and not douching or using over-the-counter vaginal deodorants.
When treating genito-pelvic pain/penetration disorder, doctors or other team members often do the following:
Encourage a woman or couple to develop satisfying forms of sexual activities that do not involve penetration and teach how to do it
Discuss emotional issues contributing to and caused by the chronic pain
When possible, treat any physical abnormality that contributes to pain (such as endometriosis or vaginal infections)
Treat involuntary contraction of the muscles in the pelvis (pelvic muscle hypertonicity)
Treat sexual interest/arousal disorders if also present
Sexual activities that do not involve penetration can help couples attain mutual pleasure (including having orgasms and ejaculation). An example is stimulation involving the mouth, hands, or a vibrator.
Spending more time in foreplay may increase vaginal lubrication and thus make intercourse less painful.
For deep pain, using a different position for intercourse may help. For example, being on top can give women more control of penetration, or another position may limit the depth of penetration.
Sometimes topical numbing gels (such as lidocaine) are prescribed for specific painful areas.
Pelvic floor physical therapy
Pelvic floor physical therapy can often benefit women with genito-pelvic pain/penetration disorder. It includes pelvic floor muscle training, sometimes with biofeedback, to teach women how to consciously relax their pelvic muscles.
Physical therapists may use other techniques to improve the function of the pelvic muscles. Techniques include
Soft-tissue mobilization and myofascial release: Using various movements (such as rhythmic pushing or massage) to apply pressure on and stretch the affected muscles or the tissues that cover muscles (myofasciae)
Trigger-point pressure: Applying pressure to very sensitive areas of the affected muscles, which may be where the pain starts (trigger points)
Electrical stimulation: Applying gentle electric current through a device positioned at the opening of the vagina
Bladder training and bowel retraining: Having women follow a strict schedule for urination and recommending exercises to strengthen the muscles around the urethra and anus, sometimes with biofeedback
Therapeutic ultrasound: Applying high-frequency sound waves to the affected muscles (increasing blood flow, enhancing healing, and making tight muscles less tight)
Levator ani syndrome (vaginismus) can be treated with progressive desensitization (done by hand or with dilators). This technique enables women to gradually get used to the genital area being touched. The next step is taken only when a woman is comfortable with the previous step.
A woman touches herself daily as close to the vagina's opening as possible. Once her fear and anxiety due to touching her genitals has decreased, A woman will be more able to tolerate the physical examination.
A woman inserts her finger past her hymen. She is instructed to push or bear down as she inserts her finger to enlarge the opening and ease entry into the vagina.
She inserts specially designed dilators gradually increasing sizes. Leaving a dilator inside for 10 to 15 minutes helps the muscles get used to gently increasing pressure without automatically contracting. After she can tolerate the smallest size, she inserts the next larger and so on.
A woman allows her partner to help her insert a dilator during a sexual encounter to confirm that it can go in comfortably when she is sexually excited.
A woman should allow her partner to touch the area around the vagina's opening with his penis or a dildo but without its entering the vagina. Then a woman can get used to feeling the penis or dildo on this area.
Eventually, a woman inserts her partner’s penis or a dildo partially or fully into the vagina in the same way that she placed the dilator. She may feel more confident if she is on top during intercourse.
For superficial pain, pelvic floor physical therapy is key because involuntary contraction of the muscles around the vagina's opening is often part of the problem. Liberally applying a lubricant before intercourse may help. Sometimes doctors suggest applying an anesthetic gel.
Psychological therapies
Psychological therapies, such as cognitive-behavioral therapy and mindfulness-based cognitive therapy, may benefit some women. Mindfulness involves focusing on what is happening in the moment, without making judgments about or monitoring what is happening. Such therapies may help a woman manage fear and anxiety about pain during sexual intercourse.
Doctors may refer women to a psychotherapist, couples therapist, or a qualified sex therapist for psychological therapies.
Drug Information for the Topic




